Qualified plastic surgeon
Verify the surgeon’s full name, recognised plastic-surgery specialty, professional registration, relevant training and privileges to perform gluteal fat grafting at the named hospital.


Explore gluteal fat grafting with clearly mapped donor areas, realistic contour goals, subcutaneous-only fat placement, real-time ultrasound guidance, verified surgeon credentials and a recovery plan built around pressure avoidance, mobility and safe travel.
A BBL uses liposuction to harvest a patient’s own fat, processes that fat and transfers selected amounts into the superficial tissue of the buttocks or hip area. Despite its name, it is not a traditional surgical lift and it does not remove loose buttock skin.
Gluteal fat grafting has a documented history of fatal fat embolism and carries significant risk compared with many elective aesthetic procedures. Final suitability, technique, volume, anaesthesia, admission, recovery and travel clearance require direct assessment by the treating surgeon and anaesthesia team.

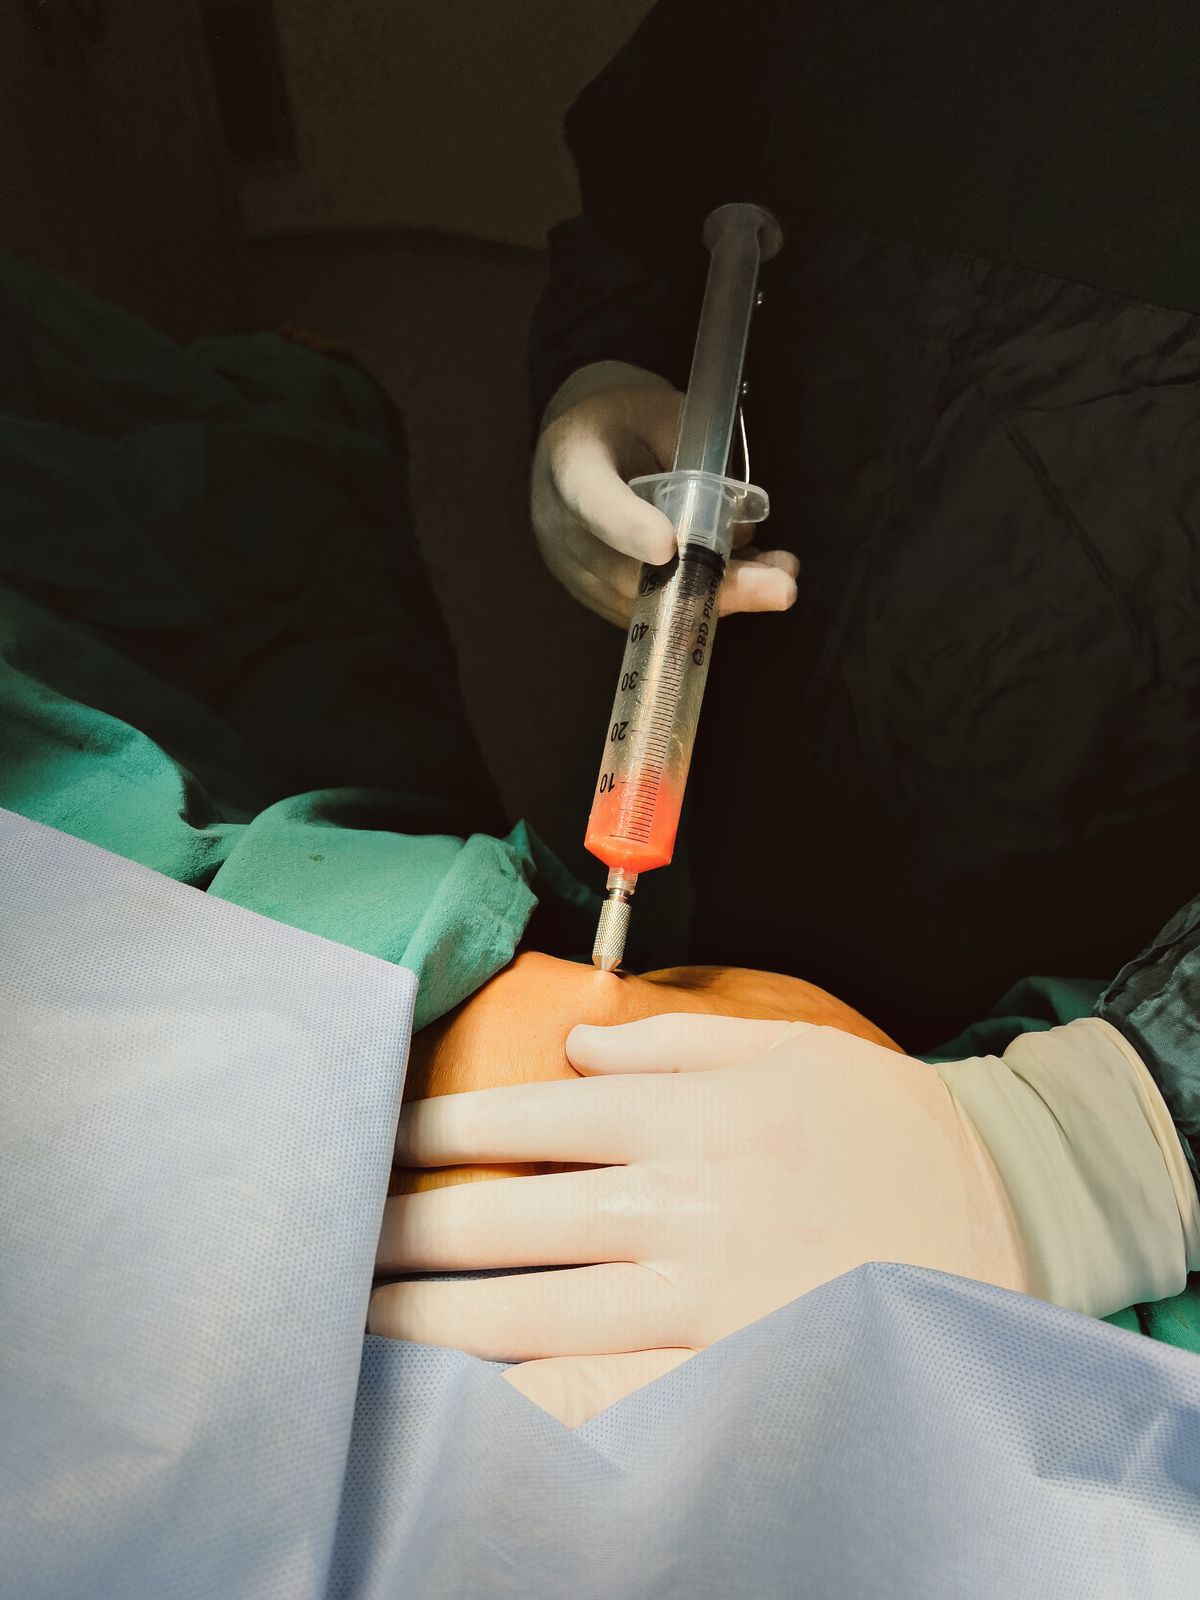
The operation begins with liposuction from individually selected donor areas—often parts of the abdomen, waist, flanks, back or thighs. Harvested fat is prepared and injected in small passes to alter selected buttock or hip contours.
The transferred fat must remain in the subcutaneous tissue above the gluteal fascia. Injection into or below the muscle can expose large veins and is associated with fatal fat embolism. International plastic-surgery societies support real-time ultrasound during injection so the surgeon can see the cannula tip and confirm the tissue plane.
The result depends on both the reduction created by liposuction and the volume that safely survives after transfer. Exact shape, symmetry, cup size or centimetre change cannot be guaranteed, and attempting an extreme increase can conflict with safe superficial capacity.
These checks do not remove all risk. They help expose whether a proposal reflects current safety recommendations or is only a marketing package.
Verify the surgeon’s full name, recognised plastic-surgery specialty, professional registration, relevant training and privileges to perform gluteal fat grafting at the named hospital.
The surgeon should state that fat will stay above the gluteal fascia. Intramuscular and submuscular injection should not be part of the plan.
Ultrasound should show the cannula tip during fat injection—not merely be available in the building or used for a brief check before or after transfer.
Confirm who performs liposuction, who injects the fat, who observes the ultrasound and whether the responsible surgeon remains physically present and attentive.
Confirm the exact branch, anaesthetist, monitoring, admission plan, blood and imaging access, resuscitation capability and transfer pathway if higher-level care is needed.
The proposed transfer must fit donor-fat availability, skin and superficial tissue capacity. A fixed large volume or celebrity shape promised before examination is a warning sign.
Fat embolism, blood clots, infection, bleeding, anaesthetic complications and other serious events can still occur. Suitability, technique, total procedure extent and aftercare remain essential.
The surgeon should assess donor areas, gluteal anatomy, health and practical recovery demands together.
 Donor-tissue context: Lucas Guimarães Bueno / Pexels
Assess the amount and quality of pinchable fat, skin elasticity, asymmetry and prior liposuction across the abdomen, waist, flanks, back and thighs. The surgeon should identify what can be removed without creating unsafe fluid shifts or irregularity.
Describe potential donor areas → Hip-proportion context, not a result: Andres Ayrton / Pexels
Assess gluteal width, projection, upper and lower pole, hip dips, pelvic and waist proportions, skin laxity, cellulite, asymmetry and the amount of superficial tissue available above the fascia.
Explain the shape—not only the size—you want assessed → Health-history discussion: Antoni Shkraba / Pexels
Disclose conditions, medicines and supplements, anaesthesia problems, allergies, bleeding or clot history, smoking or nicotine, weight changes, pregnancies and all prior buttock injections, fillers, implants, fat transfer or body surgery.
Ask how to share records securely → Surgical preparation: Zeynep Özata / Pexels
Confirm donor sites, expected ranges rather than guaranteed volumes, cannula plan, ultrasound device and user, surgeon workload that day, anaesthesia, positioning, monitoring, admission, clot prevention and emergency pathway.
Request an individual treatment plan →Remote photographs cannot show the injection plane, tissue thickness, vein anatomy, scar quality or clot risk. The operating surgeon must re-examine you in person and may reduce, stage or decline the proposed treatment.
Each stage changes both safety and appearance. “Lipo 360” and “high-definition BBL” are marketing labels unless the exact treated areas and methods are written down.
The surgeon marks selected donor zones and uses liposuction to remove subcutaneous fat. Removal should respect skin quality, previous scars, fluid balance, blood loss and total operative extent.
Confirm: every treated area and who performs it.
Harvested material is handled to separate usable fat from excess fluid, oil and unwanted components. Processing method varies and does not guarantee graft survival.
Confirm: handling method and sterility.
The surgeon places small parcels only in the subcutaneous layer while watching the cannula tip with real-time ultrasound. Deep muscle injection should not occur.
Confirm: continuous imaging during injection.
Donor areas may need compression while the grafted area needs a specific pressure-avoidance plan. Wounds, fluid, circulation, mobility and oxygenation require monitoring.
Confirm: written sitting, sleep and garment instructions.

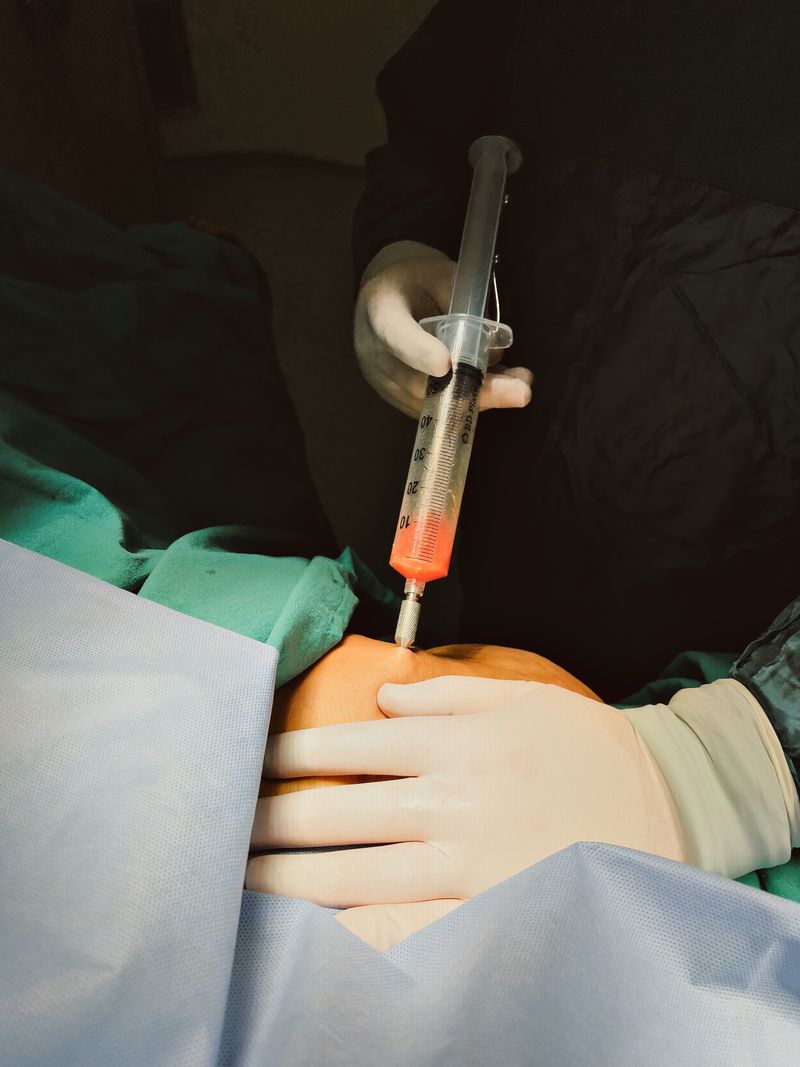
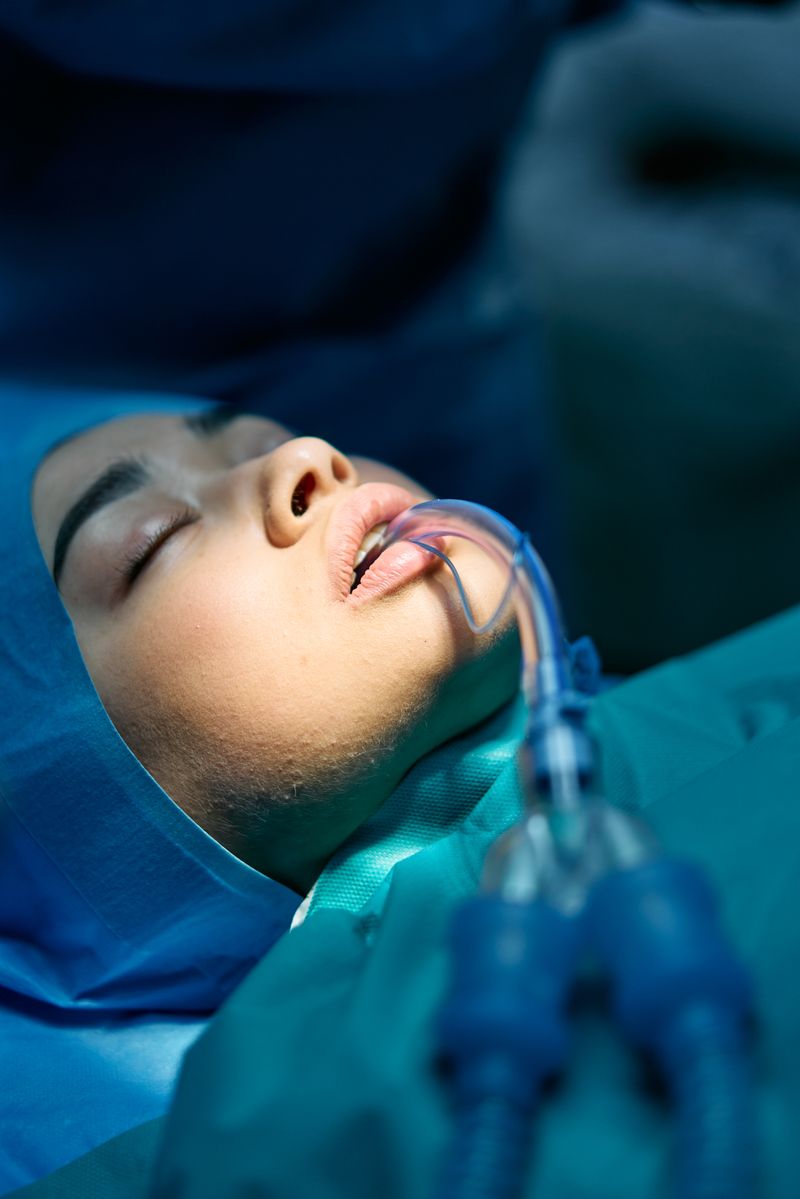
The body photographs illustrate assessment views only and are not before-and-after images. The procedure photographs show liposuction, anaesthesia and operating-room care; they do not claim to document a VIPmedi BBL case or the ultrasound-guided injection stage.
These options solve different anatomical problems and carry different risks. They are not interchangeable upgrades.
Uses a patient’s own fat to change donor-area contours and add selected superficial volume to the buttocks or hips. It requires sufficient donor fat and accepts variable graft survival.
Specific risk: fatal fat embolism if fat enters the circulation.
Can change waist, flank, back or thigh contours without injecting fat into the buttocks. It may create visual contrast but does not directly add gluteal volume.
Separate consent: donor-zone reduction is not automatically a BBL.
Excises selected loose skin and tissue, often after major weight loss. It produces longer scars and may flatten or reshape tissues rather than simply add volume.
Relevant concern: skin laxity rather than limited projection.
Implants and so-called “liquid BBL” injections involve different materials, planes and risks, including infection, displacement, wound problems, foreign-body reactions or vascular injury.
Confirm: exact product, approval status, traceability, alternatives and removal plan.
The clinical plan—not the package dates—should determine when each step occurs.
Long seated travel can add blood-clot risk and place pressure on transferred fat, while delaying travel may require longer local accommodation and support. The surgeon must balance wound status, mobility, oxygenation, clot risk, flight duration and pressure-avoidance instructions before clearing travel.
Potential candidates generally need sufficient donor fat, realistic goals within the superficial plane, stable health and weight, no nicotine exposure and the ability to follow a demanding mobility, pressure and travel plan. The treating team decides individual suitability.
Very lean patients may not have enough safe donor tissue for the desired change. Gaining weight only to create donor fat can be unpredictable and is not automatically recommended.
Major weight change can alter donor zones and grafted volume. Anaemia, diabetes, heart or lung disease, clot risk, nutrition and other conditions may affect eligibility.
Nicotine can impair circulation and healing. Follow the surgeon’s precise cessation, testing and medication instructions rather than choosing your own interval.
Previous silicone, biopolymer, filler, fat transfer or implants can distort anatomy and increase infection, inflammation or vascular risk. Product records and imaging may be needed.
The result must fit the space above the muscle. A surgeon should be willing to recommend a modest change, staged treatment or no transfer when the requested volume is unsafe.
You need help with transport, meals, permitted sitting, sleep setup, garments, walking and reviews—and immediate access to emergency assessment if symptoms occur.
VIPmedi can coordinate enquiries with participating hospitals and specialists within these partner groups. Availability, clinician, branch, technique and eligibility are confirmed individually; a logo does not mean every location offers gluteal fat grafting.
 Acıbadem
 Memorial
 Medical Park
 Medipol
 Medicana
Ask for the proposed surgeon’s name, credentials and privileges; the exact hospital branch; the real-time ultrasound device and operator; anaesthetist and monitoring; admission; emergency imaging and critical-care pathway; and who provides wound, clot and complication care after you leave Turkey.
A fixed online price cannot establish whether gluteal fat transfer is appropriate or how extensive the liposuction, ultrasound-guided transfer, monitoring and aftercare will be.
Recovery must balance donor-area healing, protection of transferred fat, frequent safe movement and monitoring for serious complications. Sitting, sleep, compression and activity instructions vary with the actual operation.
The team assesses oxygenation, heart rate, pain, bleeding, fluid balance, wounds and neurological status. Begin assisted walking only as directed.
Use the prescribed sleep and permitted sitting positions. A BBL pillow does not make unlimited sitting safe. Follow wound, medicine and garment instructions.
Walking, driving, desk work, lifting, exercise, massage, compression and direct pressure require individual clearance based on wounds and donor and grafted areas.
Swelling reduces and part of the transferred fat may not survive. Weight change can enlarge or shrink surviving fat and change both donor and grafted contours.
Call emergency services for sudden shortness of breath, chest pain, very fast heart rate, fainting, confusion, unusual drowsiness, weakness, trouble speaking, blue or grey lips, or any other sudden breathing or neurological change.
Urgent assessment is also needed for one-sided calf pain or swelling, uncontrolled bleeding, rapidly increasing swelling, severe or worsening pain, persistent vomiting or dehydration, fever, spreading redness, foul drainage, darkening skin or wound separation. Follow the treating team’s written emergency instructions.
Use the Contact Us page to describe the waist, hip or buttock features you want assessed, height and weight history, conditions, medicines and supplements, allergies, nicotine use, clot history and previous liposuction, implants, fillers, injections or fat transfer. Ask how requested standing photographs and records should be shared securely.
Fat is harvested from selected donor areas with liposuction, prepared and transferred in small passes into the superficial fatty tissue of the buttocks or hip area. It is not a traditional lift and does not remove loose buttock skin. Every injection should remain above the gluteal fascia.
The buttocks contain large veins beneath and within the muscle. If injected fat enters damaged vessels, it can travel to the lungs or other organs and cause fatal fat embolism. Major liposuction, anaesthesia, fluid shifts, infection and blood clots add further risk.
It means the graft is placed only in the fatty layer above the fascia covering the gluteal muscle. Intramuscular or submuscular injection is not part of a safety-led plan. Ask for this commitment in writing and discuss how the surgeon prevents the cannula from crossing the fascia.
Real-time ultrasound allows the surgeon to visualise the cannula tip during injection and verify that it remains in the superficial plane. It should be used throughout transfer, not simply for a preoperative scan. It reduces uncertainty but does not eliminate all risk.
There is no safe universal volume. The amount depends on donor fat, skin and superficial tissue capacity, asymmetry, fluid balance, liposuction extent and intraoperative findings. A guaranteed large volume before examination is unsafe marketing. The surgeon may recommend a smaller or staged transfer.
Possibly, if there is enough suitable donor fat for a modest goal, but some lean patients are not candidates for meaningful fat transfer. Gaining weight specifically for surgery is not automatically appropriate. Alternatives or no surgery may be safer after examination.
No. Some transferred fat is reabsorbed, and survival varies with technique, tissue, circulation, pressure, smoking, health and healing. Early swelling is not the final volume. Avoid exact survival guarantees, and do not judge a second procedure until the surgeon considers healing sufficiently mature.
Tell the surgeon exactly what was used, when and where. Obtain product labels, procedure notes and imaging if available. Unknown materials, inflammation, migration, scarring, infection or implants can make fat transfer unsafe or require separate investigation and treatment.
Potential areas include selected parts of the abdomen, waist, flanks, back or thighs, but they are not automatic. The plan depends on pinchable fat, skin quality, scars, asymmetry and safe total extent. Read the Liposuction in Turkey guide.
There is no universal schedule. Follow the operating surgeon’s written instructions for sleep position, essential sitting, toilet use, transport, pressure support and gradual return to normal sitting. A special pillow does not make prolonged or unrestricted sitting safe.
Compression may be prescribed for donor areas, with modifications to avoid unwanted pressure on grafted tissue. Small liposuction openings may drain fluid, and surgical drains are used in selected plans. Confirm fit, duration, hygiene, removal and whom to contact for swelling, pain or skin changes.
Stay through the required wound, mobility and surgeon reviews and until medically cleared. BBL adds concerns about blood clots, prolonged sitting and pressure on the graft, so a package departure date cannot determine safety. Flight duration and individual health may require a longer stay.
Sometimes, but combining procedures can lengthen surgery and create competing recovery demands: abdominal wounds need protection while direct pressure on the buttocks is restricted. Mobility and clot prevention can become harder. Ask whether separate stages are safer and read the Abdominoplasty and Mommy Makeover guides.
Confirm the named surgeon, anaesthetist, hospital and branch; donor areas; subcutaneous-only injection; real-time ultrasound use; expected range rather than guaranteed transfer volume; tests; anaesthesia; admission; garments; medicines; reviews; travel services; exclusions; emergency access and revision policy. Request complete operation and anaesthesia records before departure. Contact VIPmedi for an individual enquiry.
Tell us the contour changes you want assessed, your health and weight history, previous body treatments and when you hope to travel. VIPmedi can help coordinate the next appropriate enquiry with a participating partner hospital.
Use the contact page for your initial enquiry. Avoid sending identity documents or full medical records in the first message; ask how requested information should be shared securely.