Symptoms and daily function
Discuss driving, reading, work, mobility, glare, falls risk, hobbies and whether the current vision can be managed acceptably with updated glasses or better lighting.


Plan cataract surgery around a complete eye examination, optical biometry, corneal and retinal assessment, an individual intraocular-lens target and a documented review pathway before travelling home.
Cataract surgery removes the eye’s cloudy natural lens and normally replaces it with a clear artificial intraocular lens, or IOL. The goal is to improve vision limited by cataract—not to promise perfect vision, eliminate every pair of glasses or reverse retinal, optic-nerve or corneal disease.
Final suitability, anaesthesia, IOL model and power, astigmatism plan, one- or two-eye timing, medicines, recovery and travel clearance require assessment by the treating cataract surgeon.
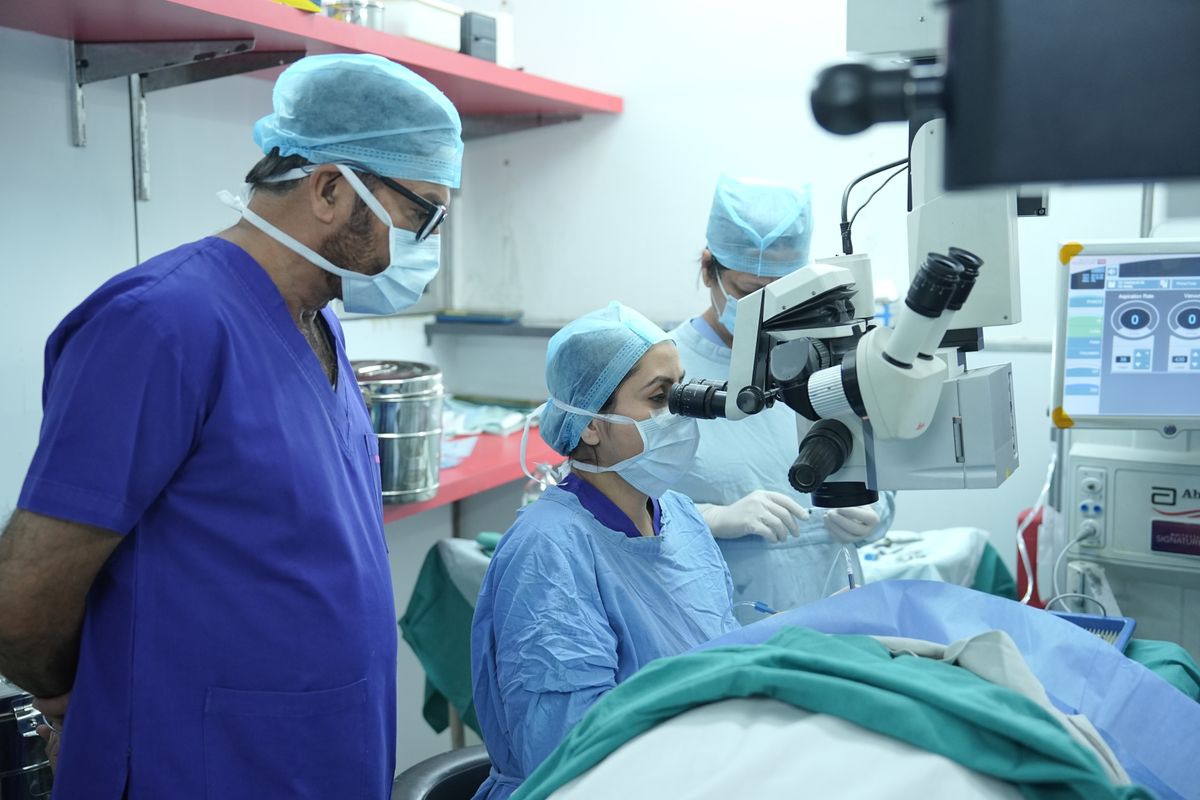

A cataract is clouding of the eye’s natural lens. Symptoms may include blur, glare, halos, washed-out colour, reduced contrast, frequent prescription change, difficulty reading or recognising faces and poorer night driving.
Surgery is generally considered when cataract meaningfully affects daily life, safety, work or examination and treatment of another eye condition. A cataract does not need to become “ripe,” but finding some lens clouding does not automatically mean surgery is necessary.
The surgeon should confirm how much of the visual limitation comes from cataract. Macular degeneration, diabetic retinopathy, glaucoma, corneal disease, amblyopia or optic-nerve damage can limit the result even when the cataract operation itself is technically successful.
No single age, visual-acuity line or lens label decides the pathway. The operating ophthalmologist should interpret the entire examination and the patient’s priorities.
Discuss driving, reading, work, mobility, glare, falls risk, hobbies and whether the current vision can be managed acceptably with updated glasses or better lighting.
Confirm that lens clouding explains the visual complaint and assess cataract density, pupil dilation, prior trauma, small pupils or other features that may alter surgical complexity.
Macular, diabetic, retinal or glaucoma disease may limit potential vision and influence timing, IOL choice, additional imaging and the need for another specialist.
Dry eye, corneal scarring, keratoconus, endothelial weakness and previous LASIK or other corneal surgery can affect measurements, healing and the accuracy of lens power.
Review glaucoma, uveitis, pseudoexfoliation, weak zonules, previous vitrectomy, high myopia, shallow chambers and medicines associated with poor pupil dilation.
Consider diabetes control, infection, anticoagulants, ability to lie still, anaesthesia needs, medication adherence, support at home and access to urgent ophthalmic review.
Dry eye, contact-lens wear, prior refractive surgery and inconsistent fixation can reduce measurement accuracy. Treat or repeat when data do not agree.
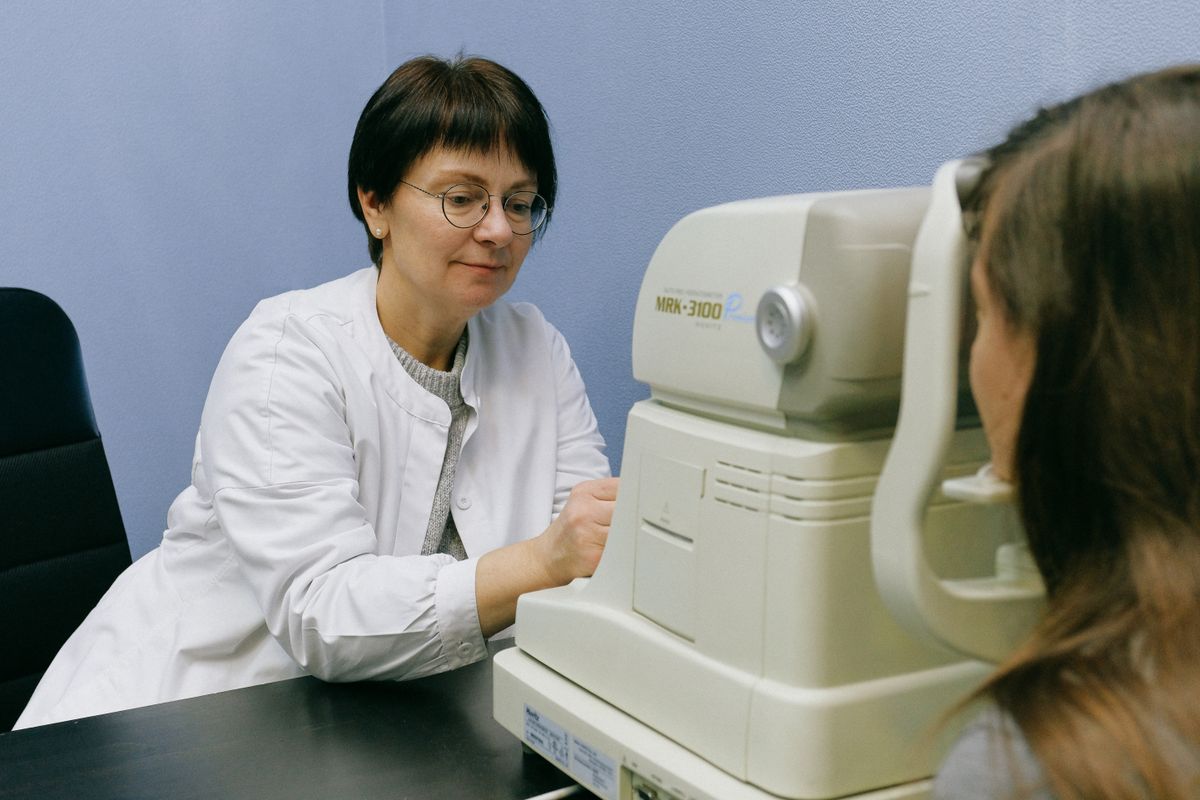
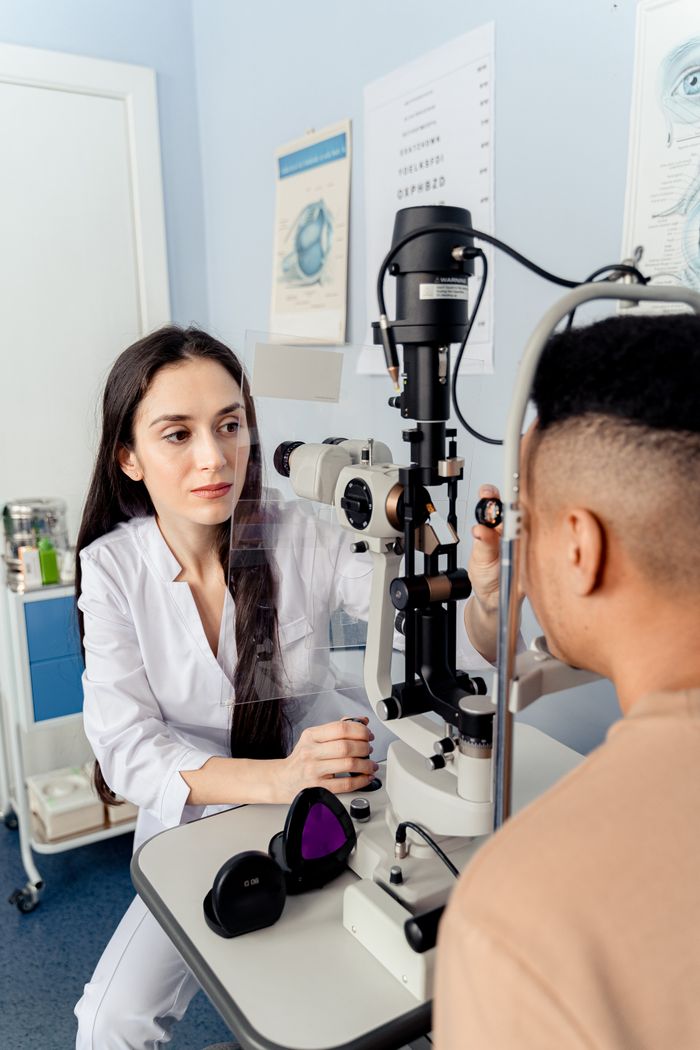 Slit-lamp examination: Antoni Shkraba / Pexels
Measure uncorrected and corrected vision, refraction and pressure; examine the cataract, cornea, pupil and eye structures and review symptoms, previous procedures, medicines and visual goals.
Ask how to share records securely → Diagnostic-equipment context: Ksenia Chernaya / Pexels
Measure axial length and corneal power, check signal quality and use an appropriate formula to estimate IOL power. Previous laser surgery or unusual anatomy requires specialised calculation.
Ask which measurements are included →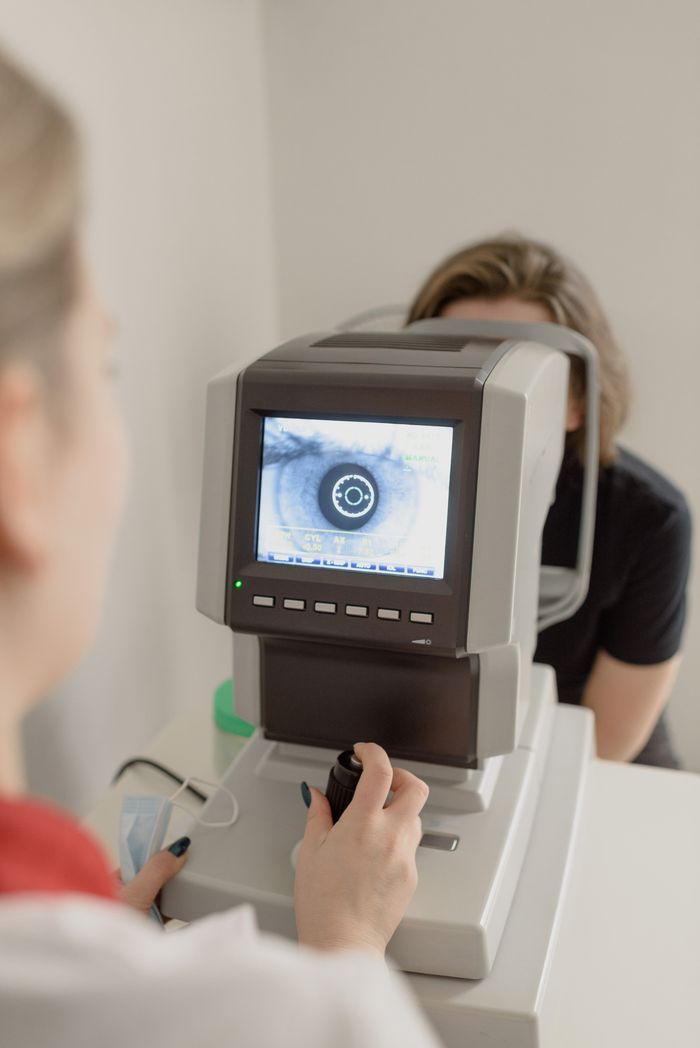 Ophthalmic imaging context: Ksenia Chernaya / Pexels
Assess tear quality, corneal curvature and astigmatism; use topography or tomography when indicated. Plan whether glasses, incision strategy or a toric IOL will address astigmatism.
Describe prior corneal treatment →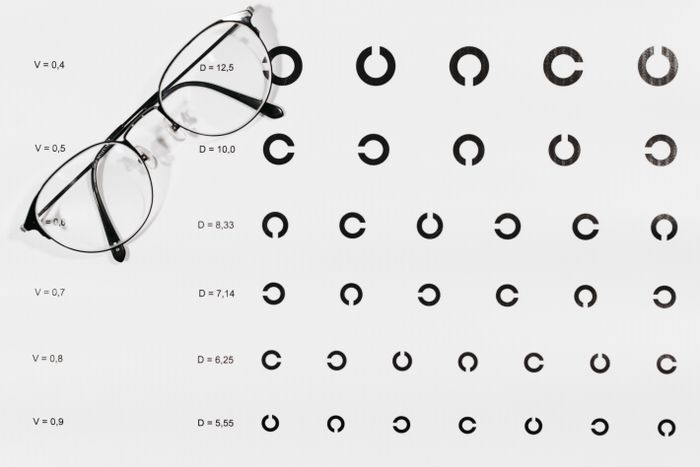 Visual-goal context: Pavel Danilyuk / Pexels
Perform a dilated examination and OCT or other testing when indicated. Identify macular, retinal or optic-nerve disease that could limit vision or make a presbyopia-correcting lens unsuitable.
Request an individual lens discussion →A remote quote based only on age or prescription cannot determine cataract severity, visual potential or the correct IOL. Final measurements and the operating surgeon’s examination must come before consent.
Technique and anaesthesia vary. Modern surgery is commonly performed through small corneal incisions while the patient is awake with local anaesthesia and monitoring.
The team repeats identity, eye, lens and power checks; dilates and cleans the eye and gives anaesthesia. Sedation or another anaesthetic approach may be used when appropriate.
Confirm: surgeon, eye, IOL model, power and target.
The surgeon enters through the cornea and opens the front of the lens capsule. Pupil-expansion or capsular-support devices may be required in more complex eyes.
Confirm: complexity factors and contingency plan.
In phacoemulsification, ultrasound fragments the cloudy lens and irrigation and aspiration remove it while preserving the capsule when possible.
Confirm: phaco plan and additional procedures.
A folded IOL is normally placed inside the remaining capsule and unfolded. The surgeon checks position, wound sealing and the eye before applying medicines and a shield.
Confirm: implant card, drops and first review.
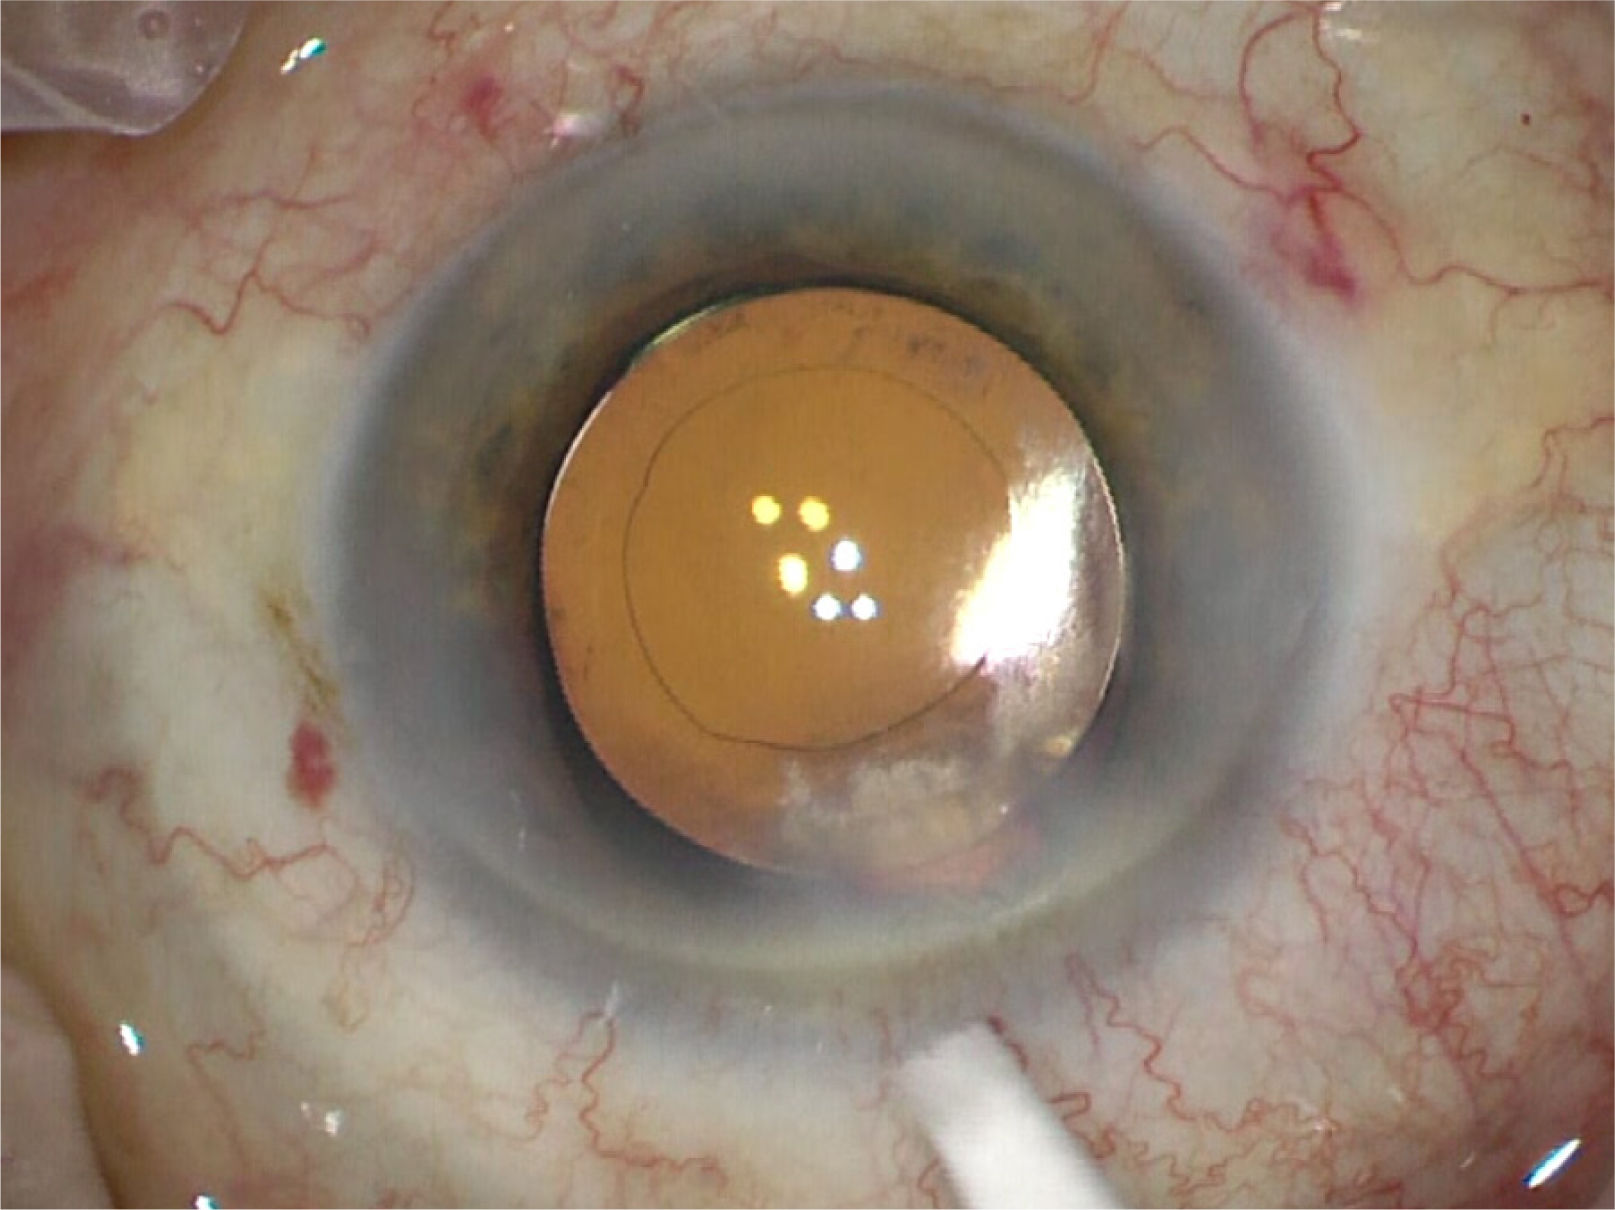
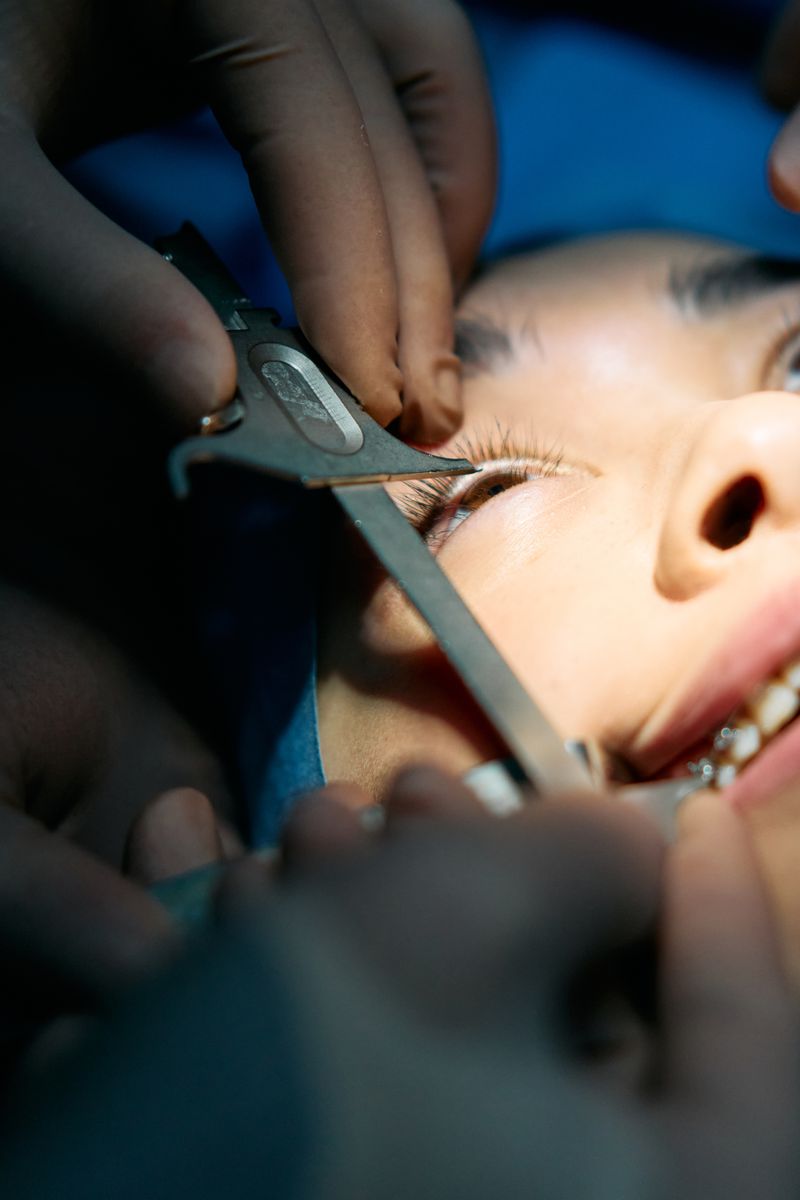
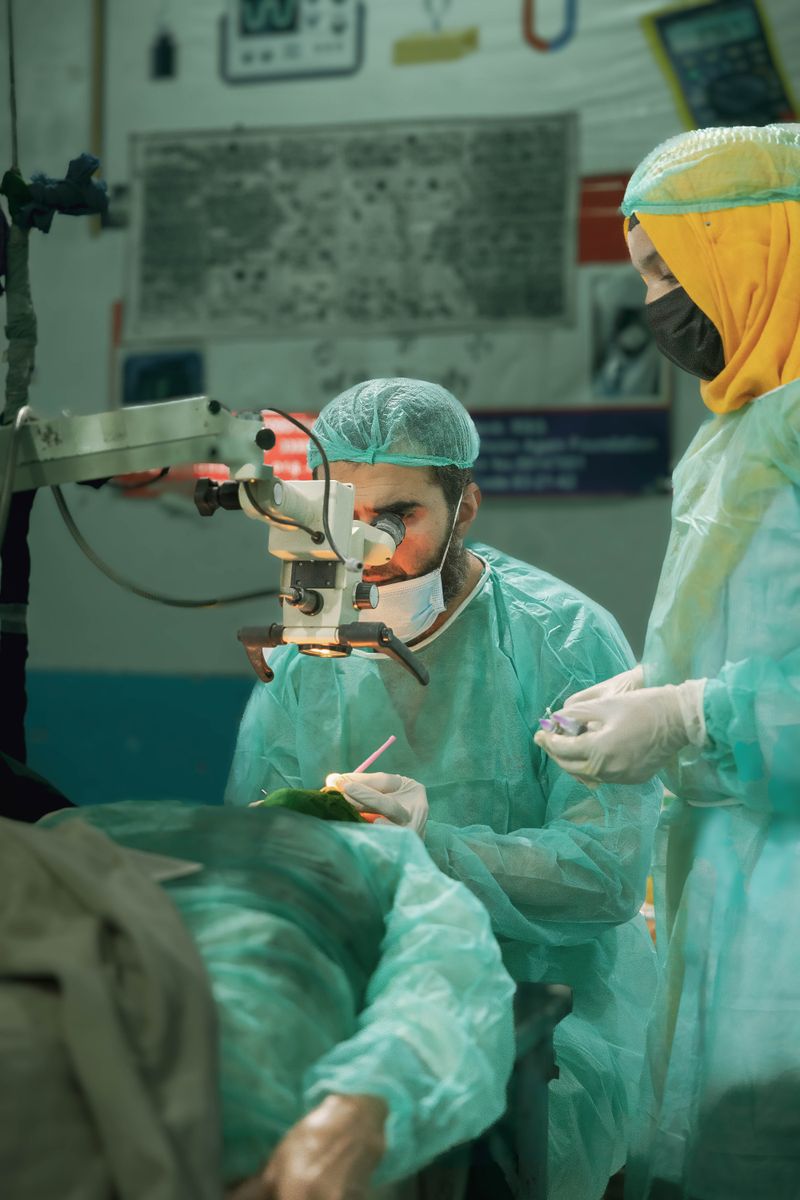
The gallery uses real ophthalmic-surgery photography and an authentic intraoperative IOL image. It does not depict VIPmedi cases, partner facilities or promised results.
The right strategy depends on eye health, corneal astigmatism, measurements, previous surgery, reading and driving priorities, tolerance of optical side effects and willingness to use glasses.
A monofocal lens is normally targeted mainly for distance, intermediate or near vision. Glasses are commonly still required for other distances and sometimes for the target distance.
Discuss: distance target, near needs and residual astigmatism.
A toric lens adds correction for suitable corneal astigmatism. Accurate measurements and alignment matter; residual astigmatism, lens rotation and glasses may still occur.
Discuss: corneal measurements, axis, rotation and backup plan.
These lenses aim to reduce dependence on glasses across more than one range. Halos, glare, contrast trade-offs, residual prescription and eye-health limitations require careful selection.
Discuss: night driving, retina, cornea and realistic spectacle use.
One eye is targeted farther and the other somewhat nearer, often using monofocal lenses. Adaptation, binocular balance and depth perception differ between people.
Discuss: eye dominance, trial experience and occupational needs.
Ask for the manufacturer, exact model, optical design, regulatory status, material, target, expected glasses use and alternatives. More focal points do not automatically mean better vision for a particular eye.
Preliminary records can help plan the visit, but final suitability, IOL power and surgical strategy require repeatable in-person measurements and examination.
Remain for the required early review and travel only when the surgeon confirms that recovery is stable. Do not drive while dilated, sedated or visually unsafe. A complication, combined retinal procedure or gas bubble can change flying restrictions completely.
The surgeon should explain personal risk, the effect of other eye disease, the possibility of additional treatment and what happens if the planned IOL cannot safely be placed.
Endophthalmitis is uncommon but sight-threatening. Increasing pain, redness, discharge, light sensitivity or deteriorating vision requires urgent ophthalmic assessment.
Corneal oedema, retinal or macular swelling and raised or low eye pressure can blur vision and may require drops, injections, laser or further surgery.
The capsule can tear or supporting fibres can fail. Lens material may move backward, a different IOL position may be needed and retinal surgery may be required.
New flashes, many floaters, a curtain, shadow or sudden visual loss needs urgent examination. Risk varies with factors including high myopia and previous retinal history.
Residual short- or long-sightedness, astigmatism, lens rotation, decentration or an unwanted visual target can require glasses, laser correction or lens repositioning or exchange.
Glare, halos, arcs, shadows, contrast change or double vision may occur. Retina, optic nerve, cornea or amblyopia can limit improvement despite successful cataract removal.
VIPmedi can coordinate enquiries with participating ophthalmology and cataract teams within Acıbadem, Memorial, Medical Park, Medipol, Medicana and Dünyagöz. The branch, operating surgeon, examination, IOL inventory and procedure are confirmed individually.
 Acıbadem
 Memorial
 Medical Park
 Medipol
 Medicana
 Dünyagöz
A group logo does not mean every branch offers every IOL, device or complex-cataract service. Ask for the exact hospital and surgeon, diagnostics, named implant manufacturer and model, regulatory status, biometry and formula strategy, retinal backup, anaesthesia pathway, early reviews and complication arrangements.
A headline amount may cover only a routine operation with a basic lens. An individual estimate should reflect eye complexity, diagnostics, exact implant, one- or two-eye timing and follow-up.
The treating team’s instructions override general timelines. Early blur or irritation can occur, but worsening symptoms require assessment rather than assumption.
Arrange transport, use the shield as instructed and begin prescribed drops. Do not rub the eye, drive or make important visual judgments while dilated or sedated.
Attend the required examination even when vision feels improved. The clinician checks healing, inflammation, pressure, cornea, IOL position and retina as indicated.
Follow individual rules for washing, make-up, bending, lifting, exercise, swimming, dust, work and driving. Do not alter prescribed drops without advice.
Arrange final glasses when advised and continue retinal, glaucoma or diabetic-eye monitoring. Posterior capsule opacity may develop later and can often be treated by laser.

Follow emergency instructions for sudden or rapidly worsening vision, severe or increasing pain, increasing redness, discharge, marked light sensitivity, injury, nausea with eye pain or any symptom that is getting worse rather than better.
New flashes, a sudden increase in floaters, a curtain or shadow, distortion or central blur also needs urgent assessment. Contact VIPmedi for coordination support, but use emergency eye services when the situation is time-critical.
Use the VIPmedi contact page. Include your age, symptoms, affected eye, current prescription, eye diagnoses and previous procedures, health conditions, medicines, allergies, visual priorities and preferred travel period. Ask how scans and clinical records should be shared securely.
A cataract is clouding of the eye’s natural lens. It can cause blur, glare, halos, faded colour, poor contrast, prescription changes and difficulty with reading, faces or night driving. Cataracts often develop with age but can also be associated with diabetes, medicines, trauma, inflammation or previous eye surgery.
The decision is normally based on how vision affects daily life, safety, work or another eye treatment—not on a requirement that the cataract become “ripe.” The surgeon should confirm that cataract explains the visual problem and that likely benefit justifies risk. Some cataracts can be monitored when symptoms are manageable.
Updated glasses and lighting may help temporarily, but they do not clear the cloudy natural lens. Established cataract treatment removes the clouded lens surgically and usually replaces it with an IOL. A laser may assist selected surgical steps or treat posterior capsule opacity later; it does not make the original cataract transparent again.
The surgeon normally makes small corneal incisions, opens the front capsule, breaks and removes the cloudy lens—commonly using phacoemulsification—and places a folded IOL inside the remaining capsule. Technique changes when the pupil is small, the capsule or zonules are weak or another eye condition requires treatment.
Many operations use anaesthetic drops or a local anaesthetic while the patient remains awake, sometimes with sedation. Pressure, bright light, movement or unusual sensations may be noticed. General anaesthesia or another approach may be considered for selected patients. Severe or increasing postoperative pain requires urgent advice.
Optical biometry measures eye length and corneal power, and a calculation formula estimates the implant power for the agreed visual target. Dry eye, irregular cornea, extreme eye length and previous LASIK or other refractive surgery can reduce predictability and may require specialised measurements and formulas.
A monofocal IOL has one main focal target. A toric IOL adds correction for suitable corneal astigmatism. Multifocal or trifocal designs distribute focus across multiple ranges, while extended-depth-of-focus designs aim to broaden a range. Optical trade-offs, terminology and performance vary by model; ask for the exact lens rather than a marketing category.
Possibly. Glasses needs depend on the target, IOL design, residual prescription and astigmatism, healing and eye health. Even a presbyopia-correcting lens cannot guarantee complete spectacle independence. Decide which distances matter most and which optical side effects or compromises you are willing to accept.
Practice varies. Many pathways operate on separate dates, allowing the first eye to be reviewed before the second. Immediate sequential bilateral surgery may be considered in selected settings with specific safety processes. Each eye requires its own diagnosis, measurements, consent, sterile procedure and postoperative plan.
A femtosecond laser can assist selected steps, while phacoemulsification uses ultrasound to remove the lens. Technology alone does not determine a better individual result. Surgeon judgment, eye complexity, IOL selection, accurate measurements, sterile technique, complication management and aftercare remain central. Ask what practical benefit the laser is expected to provide for your eye.
Potential complications include infection, severe inflammation, bleeding, pressure change, corneal or macular swelling, capsular rupture, retained or dropped lens material, retinal tear or detachment, implant-position problems, refractive surprise, need for another operation and rare permanent loss of vision or the eye. Personal risk depends on the eye and health history.
The removed natural lens cannot grow back. The capsule supporting the implant may become cloudy months or years later; this is posterior capsule opacity, sometimes called a “secondary cataract.” When clinically appropriate, it is commonly treated with a separate YAG laser opening after the surgeon checks the eye and retina.
Do not drive while dilated, sedated, blurred or until the treating team confirms that vision meets the applicable legal and safety standard. Remain in Turkey through the required early review and fly only when recovery is stable and the surgeon clears travel. Complications or a combined retinal operation may require a different timetable.
Confirm the hospital, surgeon, eye, procedure, IOL manufacturer, model and target, diagnostics, anaesthesia, medicines, reviews, travel services, exclusions and complication policy. Keep the implant card, measurements, operative report, drop schedule, warning signs and named contacts. Contact VIPmedi for an individual enquiry.
Tell us about the affected eye, symptoms, current glasses, previous eye diagnoses or surgery, medicines, visual priorities and preferred travel period. VIPmedi can help coordinate the next appropriate enquiry with a participating partner hospital.
Use the contact page for your initial enquiry. Avoid sending identity documents or complete medical records in the first message; ask how requested information should be shared securely.