Six-implant full-arch rehabilitation

All-on-6 Dental Implants in Turkey

Explore fixed full-arch treatment supported by six planned implants, with CBCT-led assessment, prosthetic-first implant distribution, written provisional and final bridge specifications, and coordinated follow-up.

All-on-6 may be considered when the anatomy and final prosthetic design support six useful implant sites, a different distribution from a four-implant plan, or selected segmented-restoration options. Six is not automatically safer, longer-lasting, or better than four or eight implants.

Six per treated archProsthetic-first planningNo automatic upgrade

Suitability, implant number and position, extractions, grafting, immediate loading, anaesthesia, bridge segmentation, materials, visit schedule, and aftercare are individual clinical decisions. A preliminary plan may change after examination, CBCT, or surgery.

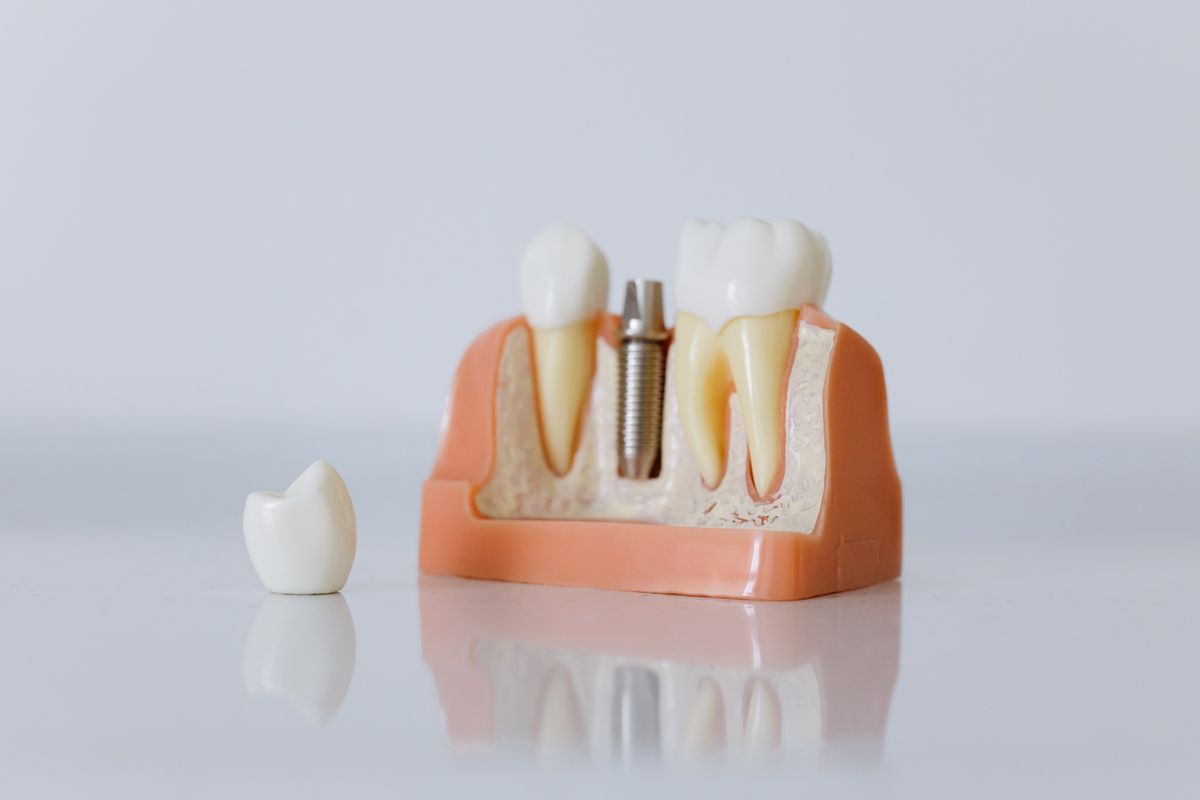
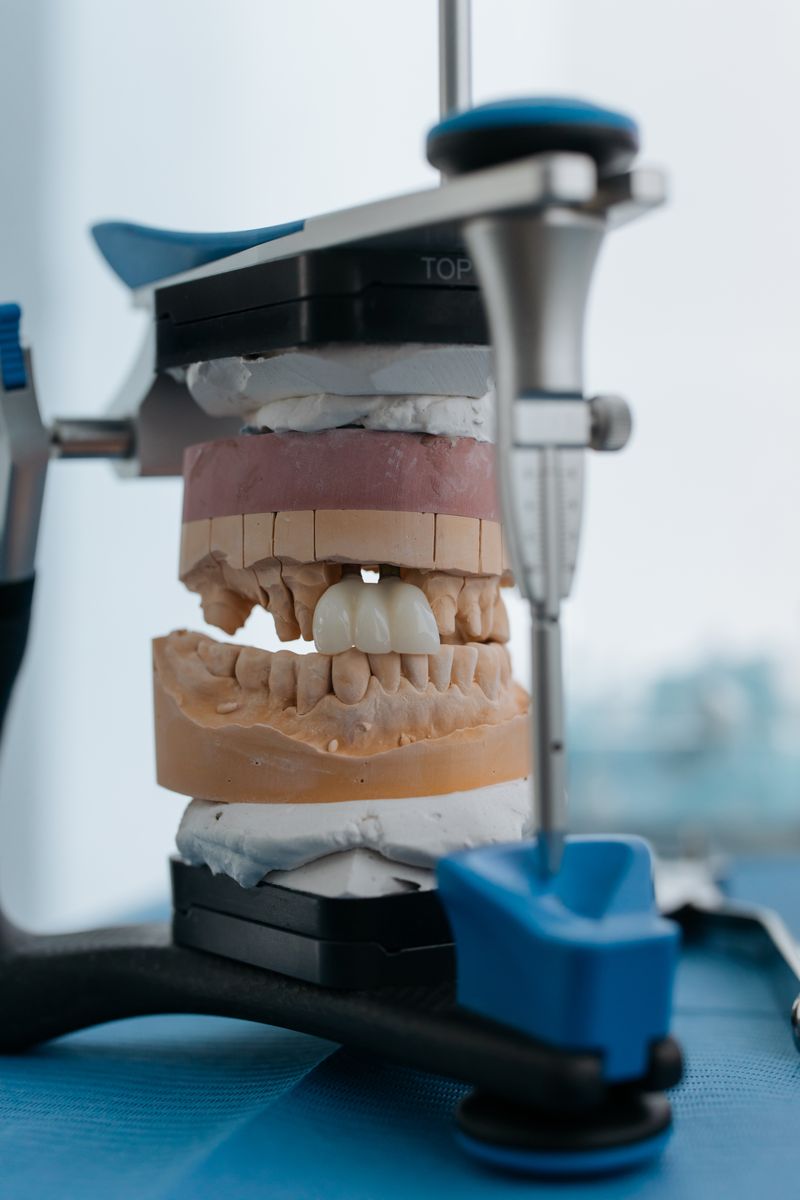
Close-up dental model showing implant-supported replacement teeth and jaw structure
Implant-supported teethPhoto by cottonbro studio / Pexels. Editorial illustration; not a VIPmedi case, partner facility, treatment, or result.
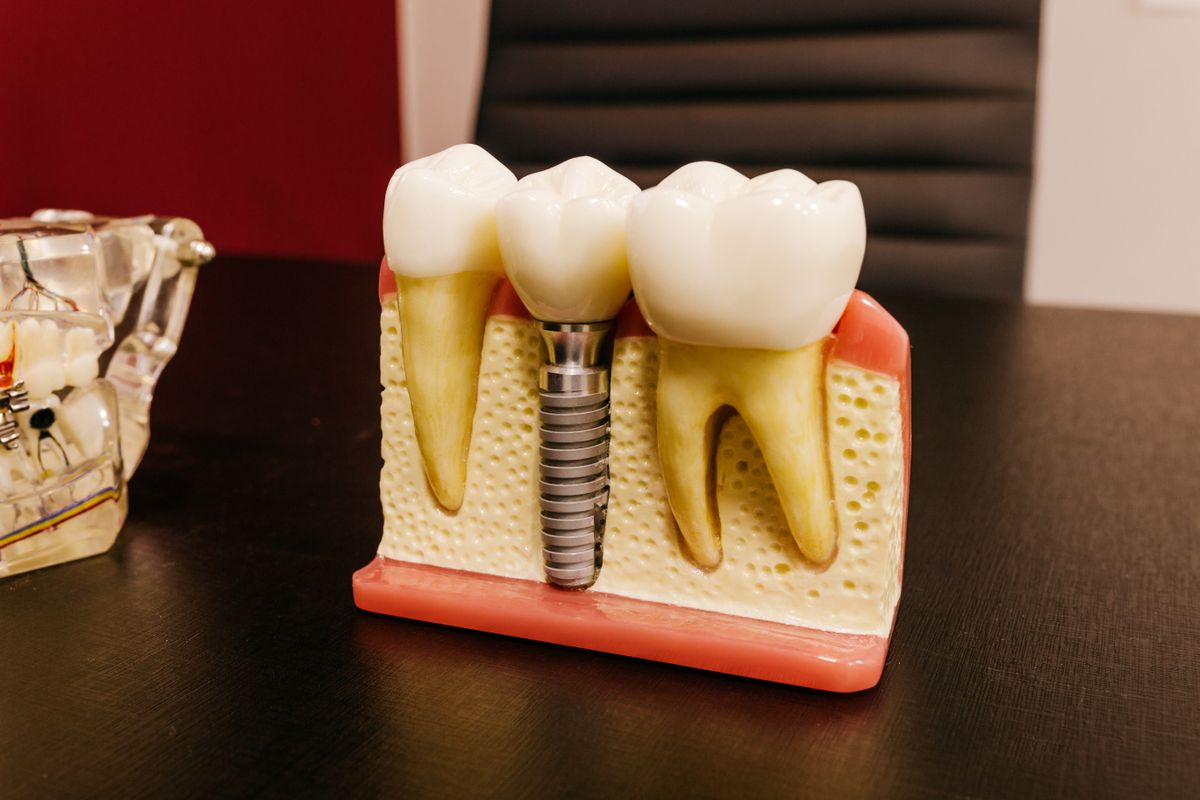
Dental implant components and prosthetic model arranged on a clinical work surface
Implant components: Jonathan Borba / Pexels
A complete-arch plan—not six separate crowns

What are All-on-6 dental implants?

All-on-6 commonly describes a fixed full-arch dental prosthesis supported by six implants in one treated jaw. The implants act together beneath one connected bridge or, where clinically planned, more than one bridge segment.

The term does not define one universal implant layout, loading protocol, bridge material, or brand. Two clinics can both quote “All-on-6” while proposing different implant systems, positions, grafting, provisional pathways, bridge designs, and maintenance arrangements.

Treating both upper and lower jaws normally requires a separate clinical and restorative plan for each arch. Confirm whether every quoted item applies to one arch or both.


The number is only one part of the reconstruction

What do six implants actually support?

A useful written plan separates the fixtures in the bone, connecting components, early provisional teeth, and definitive full-arch prosthesis.

In one treated jaw

Six planned implants

Implant positions should follow the intended teeth, anatomy, bone, restorative space, hygiene access, and distribution—not equal spacing on a generic diagram.

Confirm: site, dimensions, system, manufacturer, and the reason for every implant.

Between implant and bridge

Prosthetic components

Abutments, screws, cylinders, or other connectors link the prosthesis to the implants. Their compatibility, angulation, access, and replaceability affect future maintenance.

Confirm: component type, retention method, and local availability.

During healing

Provisional teeth

A fixed provisional may be attached only when the team’s loading criteria are met. With six sites, stability and surgical findings still need evaluation implant by implant.

Confirm: immediate-loading criteria and the backup healing prosthesis.

Definitive restoration

One or more bridge segments

The final design may be one connected arch or planned segments. Framework, tooth and gum material, passive fit, cleansability, speech, lip support, bite, repair, and retrievability matter.

Confirm: segmentation, material, laboratory, reviews, and remake terms.

“Six implants” is not a complete treatment specification. Ask the team to document why six are planned, how they will be distributed, whether the bridge is one-piece or segmented, and how the reconstruction would function if one implant cannot be placed or later fails.
Diagnosis before implant count

Four parts of a responsible All-on-6 assessment

Remote photographs and existing X-rays can support an initial discussion, but a final six-implant plan normally requires an in-person examination and three-dimensional imaging when indicated.

Teeth, gums & infection

The team assesses every remaining tooth, previous treatment, decay, fractures, gum disease, infection, and whether teeth can reasonably be preserved. A larger implant plan should not justify avoidable extractions.

Ask for a tooth-prognosis review →

Health & healing factors

Medical conditions, allergies, medicines, smoking, diabetes control, immune or healing disorders, previous radiotherapy, and antiresorptive or anticoagulant medicines may alter risk and timing. Do not stop prescribed medicine unless your own clinician directs you.

Share relevant history securely →

Bone, anatomy & distribution

CBCT-led planning reviews ridge shape and bone, sinus and nasal anatomy, mandibular nerves, restorative position, and whether six useful sites exist. Increasing implant number or spread may require grafting rather than avoid it.

Request imaging-led planning →
Dental laboratory technician crafting a full-arch prosthesis with precision instrumentsProsthesis fabrication: Ivan Babydov / Pexels

Face, bite & maintenance

Jaw relationship, bite force, grinding, smile line, lip support, speech, available bridge space, opposing teeth, manual ability, and access under the prosthesis influence both implant distribution and bridge design.

Discuss the restorative plan →

After complete assessment, the appropriate plan may use four, six, eight, or another number of implants; one or more bridge segments; an overdenture; conventional dentures; individual implants; grafting; treatment of natural teeth; or no implant surgery.

Why six may—or may not—fit the plan

Implant distribution must serve the final prosthesis

Compared with a four-implant concept, two additional well-positioned fixtures may change implant distribution, cantilever planning, or restorative options in selected anatomy. They also add surgical sites, components, cost, and maintenance considerations.

01

Distribution—not arithmetic

Two additional implants help only when placed in restoratively useful positions. The team should show the anterior-posterior spread, intended tooth position, cantilever, and anatomical limits.

02

Restorative flexibility

Six implants may support a one-piece full-arch bridge or selected segmented designs. Passive fit, screw access, cleansability, repair, and retrievability need prosthodontic planning.

03

No proven number-only upgrade

A systematic review comparing four and six implants in maxillary fixed complete prostheses found no significant difference in survival or technical, mechanical, and biological complications. Individual design still matters.

Evidence does not support choosing six from the number alone. Professional consensus recommends that implant count follow the final prosthetic plan, anatomy, implant distribution, cantilever, hygiene space, patient preference, and the consequences of future implant complications.
Compare clinical designs—not package tiers

All-on-4, All-on-6, All-on-8, or another pathway?

The appropriate number depends on the treated arch, available sites, final prosthesis, loading plan, hygiene, future repair strategy, and informed patient preference.

Four implants

All-on-4

A one-piece fixed bridge supported by four appropriately distributed implants. Tilted posterior placement may help selected anatomical situations.

Question: why are four sufficient for this arch and what is the contingency if one implant is lost?

Six implants

All-on-6

Six implants may offer a different distribution and restorative plan where six suitable sites are available. It is not automatically superior to four.

Question: what case-specific benefit do the two additional implants provide?

Eight implants

All-on-8

Eight implants may be considered for wider distribution or additional segmented-bridge options when anatomy, restorative space, hygiene, and surgical requirements support the design.

Question: why would eight be preferable to six, and would it require grafting or more surgery?

Preserve or use a removable design

Other pathways

Treating maintainable teeth, individual implants, an implant overdenture, conventional bridges, or dentures may better match some patients’ health, anatomy, hygiene, budget, or preferences.

Question: what are the benefits, risks, maintenance, and no-treatment consequences of each option?

A diagnosis-led, staged pathway

How All-on-6 treatment is commonly organised

The exact sequence and travel schedule depend on tooth prognosis, grafting, health, surgical findings, stability at all required sites, bridge design, laboratory workflow, and review criteria.

01AssessmentHistory, examination, tooth and gum prognosis, photographs, scans, panoramic imaging, CBCT when indicated, and options discussion.
02Prosthetic-first planImplant sites and number, bridge position and segmentation, extractions, grafting, anaesthesia, loading, materials, risks, and contingency decisions.
03SurgeryPlanned extractions and implant placement; grafting, bone shaping, or other procedures only when clinically indicated and consented.
04Provisional & healingA fixed provisional only if loading criteria are met. Otherwise, use the agreed healing prosthesis while osseointegration and reviews continue.
05Final bridge & maintenanceHealing reassessment, definitive records and try-ins, bridge delivery, bite and hygiene checks, documented components, and lifelong reviews.
Do not choose travel dates from a generic package schedule.

An six-implant plan may involve additional surgical sites, grafting, staged healing, several restorative records, or more than one bridge segment. The clinical team should confirm visits, flexibility, and care after you return home.

Plan Your Enquiry
Six suitable sites—not simply six available spaces

Who may be considered—and what risks must be discussed

The team must assess whether extensive implant surgery and a full-arch fixed prosthesis are reasonable for the person’s health, anatomy, dental condition, hygiene ability, restorative needs, and expectations.

Possible indication

Adults missing all teeth in an arch, or with extensive tooth failure after a documented tooth-by-tooth prognosis, may be assessed for fixed full-arch rehabilitation.

Anatomical feasibility

Six restoratively useful implant sites must be compatible with bone, nerves, sinus and nasal anatomy, ridge shape, bridge space, and the planned prosthesis. Grafting may be needed.

Maintenance commitment

The person must be able and willing to clean around more implant sites and under the bridge, attend reviews, follow healing instructions, and arrange local continuity of care.

Potential surgical and healing complications

  • Pain, swelling, bruising, bleeding, infection, wound problems, and delayed healing
  • Implant instability, lack of osseointegration, implant loss, or inability to place all six as planned
  • Nerve injury or altered sensation; sinus or nasal complications; damage to nearby structures
  • Need for grafting, sinus-related procedures, bone shaping, or staged treatment
  • Anaesthetic or sedation complications, depending on technique, treatment extent, and individual health

Prosthetic and long-term limitations

More components to maintainScrews, abutments, bridge segments, access channels, and restorative materials can loosen, wear, chip, fracture, or require professional adjustment and repair.
Biological complicationsInflammation, peri-implant disease, gum or bone loss, food trapping, hygiene difficulty, and implant loss remain possible around any implant site.
Functional and aesthetic adaptationSpeech, lip support, tooth display, bridge bulk, bite, food feel, cleaning access, and opposing-tooth wear may require adaptation or adjustment.

Reasons to pause or redesign the plan

  • Active infection or untreated gum disease
  • Maintainable teeth not properly assessed
  • Health or medicine risks not coordinated
  • Six sites would require unjustified surgery
  • Insufficient bone or restorative space
  • Inability to maintain implant hygiene
  • No local follow-up or complication plan
  • No contingency if fewer implants are placed
Coordinated partner-care enquiries

Dental care through our partner groups

VIPmedi can coordinate an enquiry with participating dental services across established hospital networks in Turkey, subject to the branch, clinical team, imaging, surgical resources, laboratory pathway, and appointment availability appropriate to your case.

Acıbadem logoAcıbadem
Memorial logoMemorial
Medical Park logoMedical Park
Medipol logoMedipol
Medicana

The named hospital or clinic, branch, affiliated sub-brand, implant surgeon, restorative dentist, laboratory, implant system, bridge design, and availability are confirmed case by case. Not every branch provides every implant or full-arch service.

Itemised information by treated arch

What affects the All-on-6 treatment cost

Full-arch estimates are generally constructed per treated arch—not per tooth. Six implants do not make two quotations comparable unless they specify the same diagnostics, components, surgery, bridge design, materials, and follow-up.

Assessment and digital planningClinical and periodontal examination, photographs, panoramic imaging, CBCT when indicated, scans, diagnostic design, and surgical guide if used
Tooth and bone proceduresExtractions, infection management, bone shaping, grafting, sinus-related procedures, staging, and complexity across six planned sites
Implants and componentsActual implant number placed, named manufacturer and system, abutments, screws, cylinders, angulated parts, and replacement-part availability
Anaesthesia, facility, and teamLocal anaesthesia, proposed sedation or general anaesthesia when clinically appropriate, surgical resources, and named implant and restorative clinicians
Provisional and final prosthesesImmediate or delayed provisional plan, one-piece or segmented final bridge, framework and tooth material, laboratory, try-ins, delivery, and adjustments
Reviews, travel, and exclusionsAppointments, cleaning and maintenance, complication access, documented hotel or transfers, language support, local care, and all items not included
Ask for one itemised written plan for each arch. It should identify the team and branch, every tooth to preserve or extract, six intended implant sites, system and components, grafting, anaesthesia, what happens if fewer implants are placed, provisional pathway, final bridge segmentation and material, laboratory, visits, travel services, exclusions, and complication or remake policy.
Healing, hygiene, and continuity

Maintain every implant site and the bridge above them

All-on-6 is fixed in the mouth but not maintenance-free. Daily access under the bridge and regular professional reviews are part of treatment, and components or prosthetic materials may eventually need repair or replacement.

01Early recovery

Follow the clinical instructions

Use prescribed medicines exactly as directed, follow the clinician’s diet and cleaning plan, and avoid smoking. Do not start or stop medication without appropriate clinical advice.

02Protected healing

Respect the provisional

Follow food-texture and loading instructions during osseointegration. Report movement, fracture, bite changes, persistent numbness, increasing swelling, or worsening pain promptly.

03Daily cleaning

Reach all six sites

Use the toothbrush and bridge-cleaning aids recommended for the actual design. The team may suggest floss threaders, interdental brushes, or an oral irrigator as an adjunct.

04Long term

Review tissues and components

Plan checks of gums, bone, implants, screws, bridge segments, bite, hygiene access, wear, and grinding—both in Turkey and with an appropriately equipped local dentist.

Leave with a continuity-of-care file. Request implant labels or passport, manufacturer and component details, implant chart, X-rays and CBCT where appropriate, operative notes, graft information, provisional and final prosthesis specifications, medication and aftercare instructions, review schedule, and emergency contacts.
Seek prompt dental or medical assessment for uncontrolled bleeding, rapidly increasing swelling, fever, pus, worsening pain, persistent or new numbness, an unstable bridge or implant, or a significant bite change. Seek urgent local care for difficulty breathing or swallowing.
Quick answers

All-on-6 dental implant FAQs

How do I start an All-on-6 dental implant enquiry?

Use the Contact Us page to describe missing or failing teeth, dental and medical history, medicines, smoking, previous implants or dentures, and preferred travel period. Ask how requested photographs, X-rays, or records should be shared securely.

What does All-on-6 mean?

It commonly means a fixed full-arch prosthesis supported by six implants in one treated jaw. It is a public-facing description, not a complete specification of implant layout, brand, loading, bridge material, or segmentation.

Is it six implants total or six implants per arch?

Six implants are planned for one treated arch. If both upper and lower jaws are treated, each normally needs its own assessment, implant set, surgical plan, and prosthesis. Confirm whether every estimate is for one arch or both.

Does every implant receive a separate crown?

Usually no. The implants support a connected full-arch bridge or planned bridge segments. Ask for a diagram showing implant sites, bridge divisions, screws, materials, and cleaning access.

Is All-on-6 automatically better than All-on-4 or All-on-8?

No. Evidence and professional consensus do not support selecting the number as a quality tier. The correct count follows anatomy, implant distribution, final prosthesis, available space, cantilever, hygiene, loading, complication planning, and patient preference.

Why might a team recommend six implants?

Possible reasons include a different anterior-posterior distribution, cantilever plan, or restorative and segmentation options compared with four implants when six suitable sites exist. The team should explain the benefit on your design and whether extra sites require grafting or additional surgery.

Will all my remaining teeth be extracted?

Not automatically. Every remaining tooth should receive a documented prognosis. The dentist should explain which teeth are maintainable, which are not, why extraction is proposed, and the alternatives.

Does All-on-6 avoid bone grafting?

No. Creating six restoratively useful sites or a wider implant distribution may require bone augmentation, sinus-related treatment, staging, or a different implant plan. CBCT and the final prosthetic design guide this decision.

Can I receive fixed teeth immediately?

Sometimes a provisional fixed bridge can be attached soon after surgery, but only if the team’s stability and loading criteria are met. The decision may change during surgery. Ask for the alternative if one or more implants are not suitable for immediate loading.

What happens if all six implants cannot be placed?

The written consent and contingency plan should address this before surgery. Depending on distribution and stability, the team may modify positions, graft and stage treatment, place fewer implants, change bridge segmentation, delay loading, or recommend another prosthesis. Do not accept an improvised change without an explanation.

Who may not be suitable for All-on-6?

Suitability may be affected by uncontrolled infection or gum disease, medical or medicine-related risks, poor healing capacity, smoking, unsuitable anatomy, inability to clean a complex bridge, insufficient restorative space, or lack of follow-up. An individual clinical team must assess these factors.

Is All-on-6 painful, and what anaesthesia is used?

Implant surgery is commonly performed with local anaesthesia; sedation or general anaesthesia may be considered in selected settings. Pain, swelling, and bruising vary with treatment extent and the person. The team should explain anaesthesia, recovery, prescribed medicines, and individual risks.

How long should I stay in Turkey?

The clinical team determines the schedule after assessing extractions, six intended sites, grafting, surgical complexity, provisional loading, bridge segmentation, laboratory stages, and reviews. Treatment may involve separate surgical and definitive-prosthesis visits. Keep travel flexible.

How do I clean around six implants and under the bridge?

Brush and clean under the bridge using aids recommended for its actual contours, such as a floss threader, suitable interdental brush, or oral irrigator as an adjunct. More implant sites create more areas that require access. Professional maintenance remains necessary.

What should the written treatment estimate and records include?

Confirm each arch, teeth to preserve or extract, clinician and branch, imaging, all intended implant sites, system and components, grafting, anaesthesia, contingency if fewer implants are placed, provisional pathway, bridge segmentation and final material, laboratory, visits, maintenance, travel services, exclusions, and complication or remake policy. Contact VIPmedi for an individual enquiry.

Take the next step

Let’s discuss All-on-6 dental implants in Turkey

Tell us about your teeth or dentures, relevant medical and dental history, previous imaging, and when you hope to travel. VIPmedi can help coordinate the next appropriate enquiry with a participating partner facility.

Contact VIPmedi Email: [email protected]

Use the contact page for your initial enquiry. Avoid sending identity documents or full medical records in the first message; ask how requested information should be shared securely.