Weight and metabolic health
Review BMI and trajectory together with type 2 diabetes, sleep apnoea, hypertension, fatty liver disease, joint limitations and other obesity-related conditions.


Explore sleeve gastrectomy with multidisciplinary eligibility assessment, a direct sleeve-versus-bypass decision, reflux evaluation, clearly named surgeon and hospital, structured nutrition and medication planning and lifelong follow-up after returning home.
Gastric sleeve surgery permanently removes much of the stomach and leaves a narrower, tube-shaped stomach. Food continues through the usual intestinal route, but the operation changes stomach capacity, appetite signalling and metabolic responses.
Final eligibility, procedure choice, anaesthesia, hospital stay, diet progression, medicines, supplementation, recovery and fit-to-fly timing require assessment by the treating bariatric surgeon and multidisciplinary team.
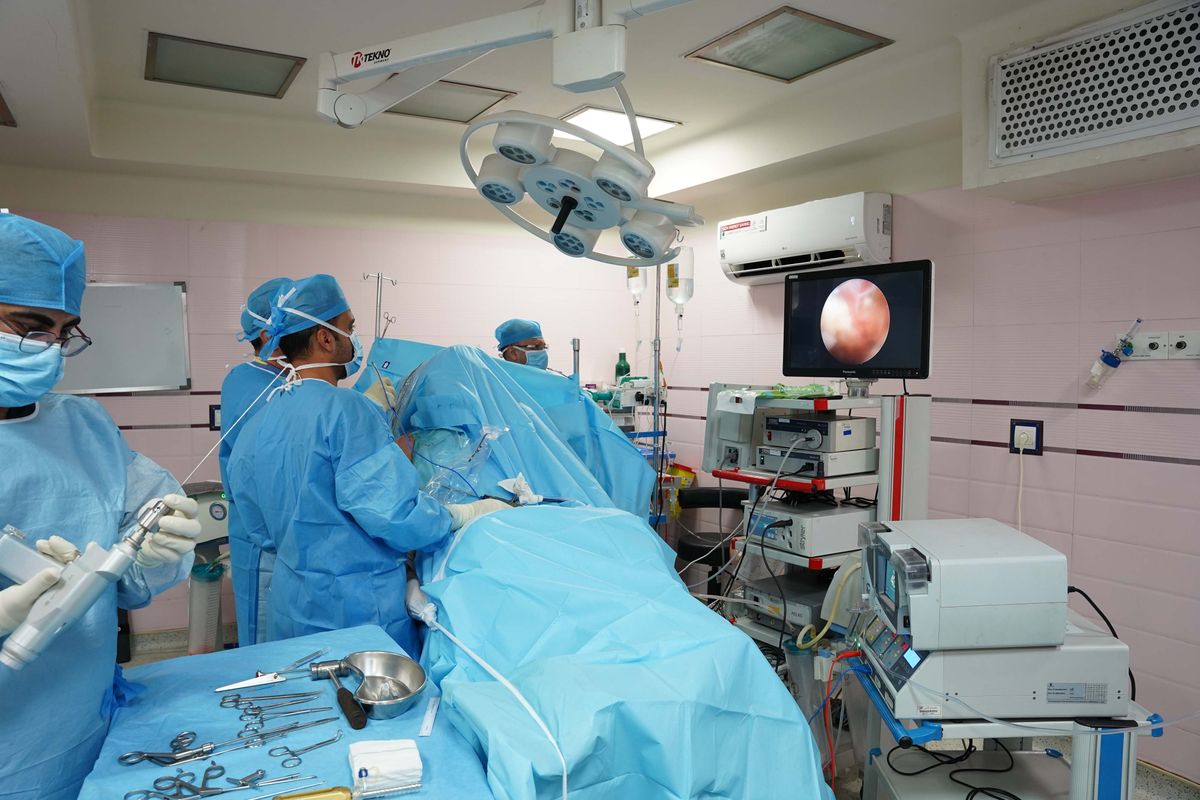
During a sleeve gastrectomy, the surgeon divides the stomach lengthwise with surgical staplers and removes the larger outer portion—commonly about four-fifths—leaving a narrow sleeve that connects the oesophagus to the small intestine through the usual route.
The removed stomach cannot be put back, so the operation is considered irreversible. It reduces the space available for food and fluid and alters appetite-related hormonal signals. It does not bypass the small intestine or place a device inside the body.
Gastric sleeve surgery can support substantial weight loss and improvement in obesity-related conditions, but it is not a guaranteed cure. Outcomes depend on health, procedure selection, eating patterns, physical activity, medicines, psychological support and long-term clinical and nutritional follow-up.
BMI thresholds and funding rules differ between health systems and may vary with ethnicity and metabolic disease. A specialist team should interpret them in the context of the whole patient.
Review BMI and trajectory together with type 2 diabetes, sleep apnoea, hypertension, fatty liver disease, joint limitations and other obesity-related conditions.
Document structured nutrition, physical activity, behavioural support and appropriate medical treatment, what helped, what did not and why weight returned.
Heartburn, regurgitation, swallowing difficulty, hiatus hernia, oesophagitis, Barrett’s oesophagus, ulcers and previous stomach surgery can change procedure choice or testing.
Assess deficiencies, meal structure, binge eating, grazing, vomiting, alcohol, sugary drinks and the ability to follow staged eating, protein, hydration and supplements.
Identify untreated mental-health needs, eating disorders, substance use, expectations, support at home and barriers to appointments or medication adherence.
Assess heart, lung, clot and airway risk, previous anaesthesia, smoking, mobility and whether coordinated dietetic, surgical, laboratory and primary-care follow-up is realistically available.
Tests should answer individual clinical questions, not be copied from a package checklist.
 Medical history discussion: Antoni Shkraba / Pexels
Review conditions, allergies, medicines and supplements, smoking or nicotine, alcohol, pregnancy plans, previous abdominal operations, endoscopy, reflux symptoms and any earlier balloon, sleeve, band or bypass treatment.
Ask how to share records securely → Clinical assessment: Antoni Shkraba / Pexels
Laboratory tests, heart and lung review, sleep-apnoea assessment, liver or gallbladder imaging, endoscopy and other tests are selected according to symptoms, conditions, medicines, age and local protocol.
Describe your conditions and previous tests → Nutrition consultation: Yaroslav Shuraev / Pexels
Correct relevant deficiencies, understand any preoperative diet, practise hydration and meal habits, plan protein and supplements and arrange appropriate psychological or eating-disorder support before surgery.
Ask about dietetic follow-up → Surgical preparation: Zeynep Özata / Pexels
Confirm surgeon and hospital branch, laparoscopic or robotic approach, hiatus-hernia plan, staple-line strategy, leak assessment, anaesthesia, clot prevention, admission, diet progression, emergency pathway and lifelong follow-up responsibilities.
Request an individual treatment plan →A video call can prepare an in-person assessment but cannot replace abdominal examination, anaesthetic review, endoscopic findings when indicated or multidisciplinary consent.
Most primary sleeves are completed laparoscopically under general anaesthesia. Robotic assistance is an access method, not a different metabolic operation and not a guarantee of a better outcome.
The team positions the patient, establishes minimally invasive access and examines the abdomen. Previous surgery or unexpected findings may change the approach.
Confirm: conversion-to-open and unexpected-finding policy.
The surgeon frees the outer stomach and uses staplers to create a calibrated tube, preserving the normal outlet into the intestine. The resected stomach is removed.
Confirm: calibration, staple-line and narrowing strategy.
The staple line is checked for bleeding, twisting, narrowing and other concerns. Leak-testing methods vary and cannot guarantee that a later leak will not occur.
Confirm: drain, imaging and leak-response pathway.
The team monitors pain, nausea, breathing, circulation, wounds and hydration. Walking and oral intake begin according to individual clinical findings and protocol.
Confirm: discharge and readmission criteria.
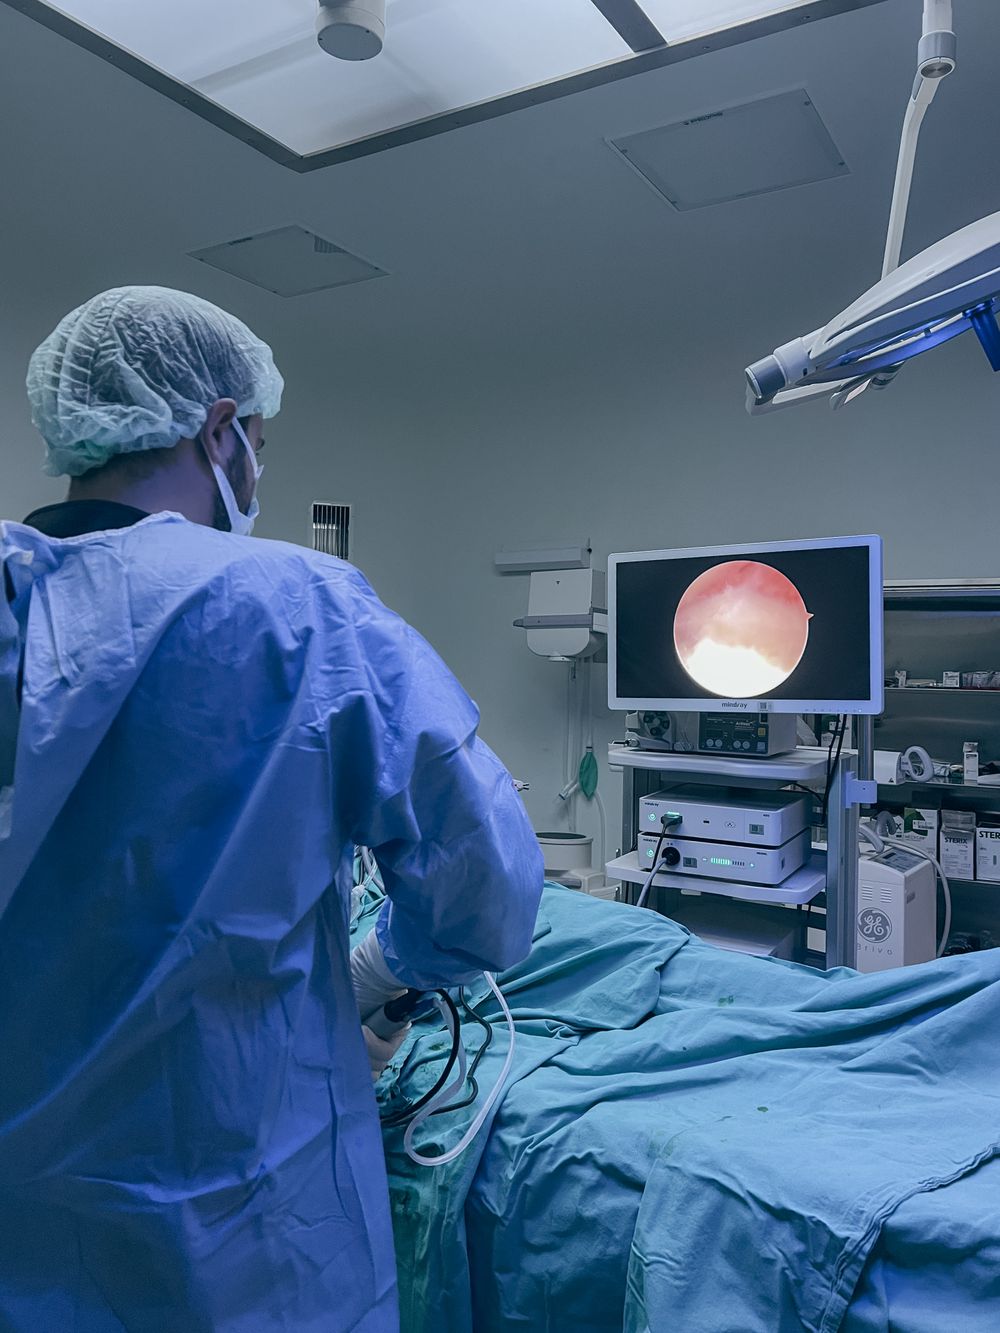


The photographs directly illustrate minimally invasive surgery, dietetic planning and clinical weight follow-up. They are editorial examples, not VIPmedi gastric sleeve cases or before-and-after results.
The appropriate pathway depends on obesity severity, metabolic disease, reflux, eating patterns, medicines, surgical risk, previous treatment and long-term follow-up—not simply the fastest advertised recovery.
Permanently removes much of the stomach and keeps food travelling through the usual intestinal route. It can support strong weight loss but may cause or worsen reflux.
Key commitment: lifelong nutrition, laboratory and weight follow-up.
Creates a small stomach pouch and a new connection to the small intestine. It may be considered for selected reflux and metabolic profiles but adds anastomosis, ulcer, internal-hernia and absorption concerns.
Compare: diabetes goals, reflux, medicines and deficiency risk.
A balloon occupies stomach space for a defined period and is later removed. It is not surgery and does not produce the same anatomical or metabolic change as a sleeve.
Confirm: device duration, removal and post-removal plan.
Structured nutrition, activity, behavioural and psychological support and appropriate medicines can be primary treatment or part of preparation and long-term care around surgery.
Reality: surgery never replaces chronic-disease management.
New or worse heartburn is a recognised sleeve concern. Symptoms, endoscopic findings and hiatus-hernia assessment must be considered before choosing sleeve; do not assume reflux can always be corrected by adding a hernia repair.
Each stage should identify the clinician responsible, the remaining decisions and the records that travel home with you.
The CDC Yellow Book advises medical tourists not to fly for 10 days after chest or abdominal surgery. Sleeve patients may need longer because hydration, oral intake, mobility, pain, wound status, clot risk and possible complications must be stable. Plan around surgeon clearance, not a package checkout date.
The team should explain immediate surgical complications, later sleeve-specific problems and the possibility of insufficient weight loss, weight recurrence or revision.
Bleeding and leakage can require urgent imaging, endoscopy, drainage, intensive treatment or reoperation. A negative intraoperative leak test does not eliminate later risk.
Persistent vomiting, pain or inability to tolerate fluids may reflect swelling, stenosis, sleeve twist or another problem and requires prompt assessment.
Sleeve can cause or worsen heartburn and regurgitation. Long-term medication, endoscopy, hiatus-hernia treatment or conversion to another operation may be considered.
Low intake, vomiting or poor adherence can cause dehydration, protein malnutrition and vitamin or mineral deficiencies. Prescribed supplements and laboratory monitoring remain necessary.
Risks include wound or internal infection, pneumonia, deep-vein thrombosis, pulmonary embolism, cardiac events, medication reactions and rare death.
Weight loss varies. Hunger, grazing, liquid calories, sleeve enlargement, biology, medicines and life circumstances can contribute to inadequate loss or regain and return of conditions.
VIPmedi can coordinate enquiries with participating bariatric teams within these partner groups. Availability, surgeon, branch, procedure and eligibility are confirmed individually; a logo does not mean every hospital provides every bariatric pathway.
 Acıbadem
 Memorial
 Medical Park
 Medipol
 Medicana
Ask for the named bariatric surgeon and multidisciplinary team, exact hospital branch, anaesthetist and facility level, test and reflux pathway, leak and bleeding response, expected admission, dietetic follow-up, emergency contact and shared-care plan after you leave Turkey.
A low headline price may omit assessment, endoscopy, treatment of other findings, longer admission, nutrition support, medicines or complication care. Compare itemised pathways rather than package totals.
The first weeks protect healing and hydration. The following years protect nutrition, metabolic health and weight outcomes.
The team monitors pain, nausea, oxygenation, circulation, bleeding and urine output. Begin walking and measured fluids only as instructed.
Follow the prescribed liquid and medication plan. Record intake if requested and report persistent vomiting, worsening pain or inability to drink.
Move through liquids, puréed or soft foods and structured solids only on the treating programme. Prioritise protein, hydration, slow eating and thorough chewing.
Continue supplements, laboratory checks, medication review, reflux monitoring, physical activity and bariatric, dietetic, psychological and primary-care follow-up.
Follow the treating team’s emergency instructions. Urgent symptoms can include a very fast heart rate, fever, increasing abdominal or left-shoulder pain, chest pain, shortness of breath, fainting, one-sided calf swelling, uncontrolled bleeding, black or bloody stool, persistent vomiting, inability to keep fluids down, very little urine, confusion, worsening weakness, spreading wound redness or foul drainage.
After returning home, tell any clinician when and where surgery occurred and provide the operation, anaesthesia, test and medication records. Bariatric complications can require specialist surgical, radiological or endoscopic treatment.
Use the Contact Us page to share height, current weight and history, obesity-related conditions, medicines and supplements, allergies, previous weight-management treatment, reflux or swallowing symptoms, abdominal operations, smoking or nicotine, pregnancy plans and preferred travel period. Ask how requested records should be shared securely.
No. The removed portion of the stomach cannot be restored. A sleeve can sometimes be converted to another bariatric operation for severe reflux, complications or inadequate metabolic or weight outcomes, but revision is a new and generally more complex operation—not reversal.
Guidelines commonly use BMI and obesity-related health conditions to trigger specialist assessment, but thresholds vary by country, ethnicity and metabolic disease. Eligibility also requires medical, nutritional, psychological and anaesthetic review and willingness to continue long-term follow-up. A BMI number alone does not approve surgery.
Sleeve removes much of the stomach while leaving the intestinal route unchanged. Bypass creates a small stomach pouch and reconnects the small intestine. They differ in reflux, metabolic effects, absorption, ulcer and anatomical risks. Read the Gastric Bypass guide.
Yes. New or worsening heartburn and regurgitation are recognised sleeve concerns. Report existing symptoms, medicines and prior endoscopy. The team may recommend endoscopy, hernia assessment or a different procedure. Persistent reflux after sleeve can require medication, surveillance or conversion surgery.
Most primary operations use laparoscopic access under general anaesthesia. The surgeon frees the outer stomach, calibrates the intended sleeve and uses staplers to divide and remove much of the stomach. The staple line is inspected for bleeding, narrowing, twist and integrity. Robotic assistance is another access method, not a different operation.
No exact number can be guaranteed. Outcomes depend on starting weight, health, biology, procedure quality, eating and activity patterns, medicines, pregnancy, psychological support and follow-up. Ask the team to explain how they report total-weight and excess-weight change and what range is realistic for your situation.
The team should reassess eating patterns, liquid calories, hunger, sleep, medicines, mental health, metabolic conditions and sleeve anatomy. Treatment may include renewed nutrition and behavioural support, appropriate medication, endoscopy or revisional surgery. Revision should follow investigation rather than blame or an automatic second operation.
The treating programme advances texture in stages—commonly measured liquids, then puréed or soft foods and later structured solids—according to healing and tolerance. Exact timing varies. Follow the dietitian’s protein, hydration, portion, chewing and meal-spacing instructions and do not advance early because you feel well.
Long-term supplementation and laboratory monitoring are needed even though the intestine is not bypassed. Reduced intake, food intolerance, vomiting and previous deficiencies can affect iron, vitamin B12, folate, vitamin D, calcium and other nutrients. Take only the prescribed bariatric formulation and schedule.
Doses may need rapid adjustment as intake, weight and blood glucose or pressure change. Do not stop insulin, diabetes, blood-pressure, anticoagulant or other medicine without direct instructions. Obtain a written medication plan for fasting, surgery, discharge and follow-up, including who reviews readings after travel.
Rapid weight loss and nutritional changes make pregnancy timing an important preoperative discussion. Follow the bariatric and obstetric teams’ individual delay, contraception, supplementation and monitoring advice. Fertility can change with weight loss, so pregnancy prevention may need review before surgery.
Stay through required oral-intake, wound and surgeon reviews and until medically cleared. The CDC Yellow Book advises no flying for 10 days after abdominal surgery, and dehydration, clot risk, pain, limited mobility or concern about a leak may require longer. Do not let a package date override clinical findings.
Seek urgent assessment for a very fast heart rate, fever, worsening abdominal or shoulder pain, chest pain, shortness of breath, fainting, calf swelling, bleeding, black stool, persistent vomiting, inability to drink, very little urine, confusion or worsening wound redness or drainage. Follow the treating team’s emergency instructions.
Confirm the named surgeon, anaesthetist, dietitian, hospital and branch; exact operation; reflux or hernia components; tests; materials; anaesthesia; admission; diet and supplements; medicines; reviews; travel services; exclusions; emergency access and revision policy. Request operation and anaesthesia records and a named shared-care plan before departure. Contact VIPmedi for an individual enquiry.
Tell us your health and weight history, previous treatment, reflux symptoms, current medicines and when you hope to travel. VIPmedi can help coordinate the next appropriate enquiry with a participating partner hospital.
Use the contact page for your initial enquiry. Avoid sending identity documents or full medical records in the first message; ask how requested information should be shared securely.